Category: Metabolic health

  • A gloved hand holds two blood sample tubes, the kind used for a high-sensitivity CRP test

    High-Sensitivity CRP: The Inflammation Number Your Cholesterol Panel Leaves Out

    High-Sensitivity CRP: The Inflammation Number Your Cholesterol Panel Leaves Out

    High-sensitivity C-reactive protein (hs-CRP) is a blood test for low-grade inflammation, read against heart risk. Under 1 mg/L is lower risk, 1 to 3 mg/L is average, and above 3 mg/L is higher. A result above 10 usually means an infection or injury, and the test is repeated once you are well.

    Normal Cholesterol, Inflamed Arteries: What Your hs-CRP Is Telling You

    A standard cholesterol panel tells you how much fuel is in the pipes. It does not tell you whether anything is burning. hs-CRP is one of the few routine tests that reads the burning, which is why it is worth understanding even if nobody has ordered it for you yet.

    Is a CRP test the same as a high-sensitivity CRP test?

    Same molecule, different range. C-reactive protein is made by the liver when the body’s inflammatory signals rise. A standard CRP test is built to catch large spikes, the kind seen with pneumonia or a flare of arthritis, where values run in the tens or hundreds. The high-sensitivity version reads the low range accurately, the region under 10 mg/L where the slow, smoldering inflammation tied to heart disease lives.

    The heart-risk bands come from a joint statement by the Centers for Disease Control and Prevention and the American Heart Association: under 1 mg/L lower risk, 1 to 3 mg/L average, above 3 mg/L higher. Measura’s laboratory panels report hs-CRP against those same bands, and flag a value above 10 for a repeat once any infection or injury has passed.

    Does inflammation cause heart attacks, or just show up next to them?

    For decades this was argued as chicken and egg. A 2017 trial settled most of it. CANTOS enrolled 10,061 people who had already had a heart attack and still had an hs-CRP of 2 mg/L or more. They received canakinumab, an antibody that blocks one inflammatory signal, interleukin-1 beta, or placebo. The drug did not lower cholesterol at all. At the 150 mg dose it still cut repeat heart attacks, strokes and cardiovascular deaths by 15% compared with placebo over a median of 3.7 years.

    It also raised the rate of fatal infections, and it is not a medicine anyone uses for prevention. Its value is the proof: turn down inflammation alone, change nothing else, and fewer arteries close. Inflammation is not a bystander at the scene. It is one of the arsonists.

    What raises hs-CRP besides the heart?

    Almost everything that makes fat sick. The usual list:

    • Visceral fat. Fat packed around the organs releases the inflammatory messengers that tell the liver to make CRP. See fat mass versus sick fat.
    • Insulin resistance. High insulin and inflammation feed each other in a loop.
    • Short or broken sleep, smoking, untreated gum disease and an inflamed gut.
    • Chronic pain and nerve injury. Damaged nerves sit in inflamed tissue, and the cytokines and chemokines released there sensitize pain fibers and keep pain going. In older adults followed for six and a half years, the link between obesity and new neuropathy ran partly through inflammatory chemokines measured in the blood.

    That last item is why pain and the heart travel together. In the UK Biobank, 475,171 adults were followed for a median of seven years. Chronic localized pain carried a 14% higher adjusted risk of cardiovascular disease and chronic widespread pain a 48% higher risk, after accounting for the usual risk factors, inflammatory diseases and anti-inflammatory medication. A person who hurts every day and has a “slightly high” hs-CRP is not describing two problems.

    Can a normal hs-CRP still miss inflammation?

    Yes, and this is the part most write-ups skip. When surgeons compared fat sampled from the surface of the heart with fat under the skin in 42 bypass patients, the heart’s fat was making far more inflammatory messengers. The authors added a warning: blood levels of inflammatory markers may not reflect the inflammation happening locally in that tissue. hs-CRP is a citywide smoke reading. A fire in one basement can burn without moving it much. That is the subject of fat around the heart.

    So a low number is reassuring, not absolving. It belongs next to waist, body composition, insulin and arterial testing, never on its own.

    What does an hs-CRP of 2 or more change?

    The 2019 American College of Cardiology and American Heart Association prevention guideline lists an hs-CRP of 2.0 mg/L or higher as a “risk-enhancing factor,” alongside metabolic syndrome, chronic inflammatory conditions and a low ankle-brachial index. In that guideline the enhancer’s main job is to tip a borderline patient toward a statin.

    The reading here is different. The statin trials proved benefit in the populations they enrolled, and those populations rarely looked like the patient with chronic pain, sick fat and three other diagnoses. An elevated hs-CRP is a question about where the fire is coming from. Lowering cholesterol in response to a fire is blaming the fire department for the fire. If you take a statin, review it with the physician who prescribed it; do not stop it on your own. But do ask what is feeding the inflammation.

    Can you bring hs-CRP down?

    Usually, by shrinking the source. In STEP-HFpEF, adults with obesity-related heart failure who lost an average of 13.3% of their body weight on semaglutide saw CRP fall by 43.5%, compared with 7.3% on placebo. The inflammation followed the fat. GLP-1 medicines may be part of your solution for specific problems, chosen after an evaluation, and the same direction can be reached by the slower road: fewer acellular carbohydrates and industrial seed oils, protein and resistance training to protect muscle, a fixed eating window, and seven to eight hours of dark, uninterrupted sleep. Each of those pushes insulin down or helps it work, and lower insulin lets inflamed fat empty.

    Dr. Padda draws his own blood during experiments on himself, because he would rather take the biological hit than recommend something he has not measured. The same rule applies to you: get the number, change one thing, and repeat it in about three months to see whether it moved.

    What should you ask for alongside hs-CRP?

    Inflammation is the last link in a chain. Ask for the earlier links too, in the order they usually move:

    1. LP-IR, the lipoprotein insulin-resistance score, which rises before HbA1c does.
    2. Fasting insulin, reported on its own and as HOMA-IR. In Dr. Padda’s clinic a fasting insulin above 10 µIU/mL is treated as high risk.
    3. GGT, an under-used early marker of fatty liver. His clinic’s risk cutoff is above 20 U/L, well under the lab’s flag.
    4. Oxidized LDL and the omega-3 index with the omega-6 to omega-3 ratio, which together read how much hyperprocessed food is in the diet.
    5. hs-CRP, read against the bands above.
    6. 25-OH vitamin D, homocysteine, and B12 with methylmalonic acid or holotranscobalamin, because a serum B12 in the normal range can still hide a deficiency that injures nerves.

    Then pair the chemistry with the body: body composition, arterial stiffness and ankle-brachial index. For how hs-CRP fits the full risk estimate, see what the ASCVD calculator misses.

    If you have chest pain, pressure, sudden shortness of breath or new weakness on one side, call 911. Measura testing is for planning, not emergencies.

    Frequently asked questions

    Should I fast before an hs-CRP test?

    Fasting does not change hs-CRP much, but it is usually drawn with fasting insulin and lipids, which do need a fast. What matters more is timing: do not test during a cold, a flare or the week after an injury, because those push the number up for reasons unrelated to your arteries.

    My hs-CRP was 12. Do I have heart disease?

    Not necessarily. A value above 10 mg/L usually reflects an infection, an injury or an inflammatory flare. The standard approach is to repeat it once you are well and read the repeat against the heart-risk bands.

    Does chronic pain raise CRP?

    It can. Painful nerve and tissue injury involve inflammatory signaling, and the conditions that feed chronic pain, such as visceral fat, insulin resistance and poor sleep, raise CRP too. A persistently elevated hs-CRP in someone with daily pain is a reason to look at the whole terrain, not just the painful spot.

    Find out where your inflammation comes from

    An hs-CRP result is a question, not an answer. Pair it with body composition, insulin and vascular testing to see what is feeding it.

    4477 Woodson Rd, Suite 201, St. Louis, MO 63134. Monday to Friday, 9:00 a.m. to 5:00 p.m. Please do not send symptoms, diagnoses or images through a web form — a website form is not a secure medical channel. Send your name and number and we will call you back.

    References

    • Pearson, T. A., Mensah, G. A., Alexander, R. W., Anderson, J. L., Cannon, R. O., Criqui, M., et al. (2003). Markers of inflammation and cardiovascular disease: application to clinical and public health practice: A statement for healthcare professionals from the Centers for Disease Control and Prevention and the American Heart Association. Circulation, 107(3), 499-511. https://doi.org/10.1161/01.cir.0000052939.59093.45 (PMID 12551878)
    • Ridker, P. M., Everett, B. M., Thuren, T., MacFadyen, J. G., Chang, W. H., Ballantyne, C., et al. (2017). Antiinflammatory Therapy with Canakinumab for Atherosclerotic Disease. New England Journal of Medicine, 377(12), 1119-1131. https://doi.org/10.1056/NEJMoa1707914 (PMID 28845751)
    • Ellis, A., & Bennett, D. L. H. (2013). Neuroinflammation and the generation of neuropathic pain. British Journal of Anaesthesia, 111(1), 26-37. https://doi.org/10.1093/bja/aet128 (PMID 23794642)
    • Schlesinger, S., Herder, C., Kannenberg, J. M., Huth, C., Carstensen-Kirberg, M., Rathmann, W., et al. (2019). General and Abdominal Obesity and Incident Distal Sensorimotor Polyneuropathy: Insights Into Inflammatory Biomarkers as Potential Mediators in the KORA F4/FF4 Cohort. Diabetes Care, 42(2), 240-247. https://doi.org/10.2337/dc18-1842 (PMID 30523031)
    • Rönnegård, A.-S., Nowak, C., Äng, B., & Ärnlöv, J. (2022). The association between short-term, chronic localized and chronic widespread pain and risk for cardiovascular disease in the UK Biobank. European Journal of Preventive Cardiology, 29(15), 1994-2002. https://doi.org/10.1093/eurjpc/zwac127 (PMID 35727954)
    • Mazurek, T., Zhang, L., Zalewski, A., Mannion, J. D., Diehl, J. T., Arafat, H., et al. (2003). Human epicardial adipose tissue is a source of inflammatory mediators. Circulation, 108(20), 2460-2466. https://doi.org/10.1161/01.CIR.0000099542.57313.C5 (PMID 14581396)
    • Arnett, D. K., Blumenthal, R. S., Albert, M. A., Buroker, A. B., Goldberger, Z. D., Hahn, E. J., et al. (2019). 2019 ACC/AHA Guideline on the Primary Prevention of Cardiovascular Disease: A Report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines. Circulation, 140(11), e596-e646. https://doi.org/10.1161/CIR.0000000000000678 (PMID 30879355)
    • Kosiborod, M. N., Abildstrøm, S. Z., Borlaug, B. A., Butler, J., Rasmussen, S., Davies, M., et al. (2023). Semaglutide in Patients with Heart Failure with Preserved Ejection Fraction and Obesity. New England Journal of Medicine, 389(12), 1069-1084. https://doi.org/10.1056/NEJMoa2306963 (PMID 37622681)

    Related reading

  • A person wraps a tape measure around their waist, the measurement that tracks belly fat better than body weight

    Obesity and Heart Disease: The Weight of Fat and the Sickness of Fat

    Obesity and Heart Disease: The Weight of Fat and the Sickness of Fat

    Obesity and heart disease are linked in two ways at once. Fat mass is a physical load: more blood to pump, a stiffer heart, a narrower airway at night. Sick fat, which doctors call adiposopathy, is a chemical problem: fat tissue that has stopped working properly and floods the body with insulin resistance, inflammation and clotting signals. A bathroom scale measures neither.

    Your Scale Can't See the Fat That's Hurting Your Heart | Sick Fat vs Fat Mass

    Most people hear “obesity raises heart risk” and picture a heavy body straining a tired heart. That is half the story, and the less dangerous half. The other half is what the fat is doing while it sits there: talking to your liver, your blood vessels, your pancreas and your nerves in a language of hormones and inflammation. Two people with the same weight can be living two very different stories, and the one with the quieter scale is sometimes the one in more trouble.

    What is the difference between fat mass disease and sick fat disease?

    In 2026 the Obesity Medicine Association published a clinical practice statement on obesity and cardiovascular disease, written by obesity medicine physicians rather than cardiologists. It runs to 26 sections, and its spine is a simple split. Obesity damages the heart directly through biomechanical “fat mass disease” and through dysfunctional fat on the heart itself. It damages the heart indirectly through adiposopathic immune and endocrine abnormalities that drive type 2 diabetes, high blood pressure, abnormal blood fats and blood clotting.

    The term adiposopathy is older than the statement. Its lead author, Harold Bays, laid it out in 2011 as “sick fat”: fat cells and fat tissue that become anatomically and functionally abnormal, and that send out the wrong endocrine and immune signals. The point of the label was to explain something that confused cardiology for years. Excess body fat does not always raise heart risk to the same degree, and in some studies heavier patients seemed to do better. Those “obesity paradoxes” become far less paradoxical once you stop asking how much fat a person carries and start asking how well that fat works.

    Think of fat tissue as a warehouse. Fat mass disease is the weight of the inventory bending the floor. Sick fat disease is the warehouse catching fire and blowing smoke into every building on the block.

    How does the weight of fat strain the heart?

    Fat is living tissue, and living tissue needs blood. The more of it there is, the more blood the heart has to move every minute. Over years, a heart that pumps against that load thickens and loses some of its ability to relax and fill. That pattern is the setup for heart failure with preserved ejection fraction (HFpEF), the kind of heart failure where the squeeze looks normal on an echo and the patient still cannot climb stairs. The OMA statement gives HFpEF, atrial fibrillation and sleep apnea their own sections for this reason.

    The load works outside the chest too. Fat around the throat narrows the airway at night, and sleep apnea pushes blood pressure up and destabilizes heart rhythm. Fat packed around the kidneys squeezes them, and the kidneys answer the squeeze by holding salt and raising pressure. Heavy legs that do not move much let blood pool in the veins, which is how clots start. None of that requires the fat to be “sick.” It only has to be there.

    How does sick fat inflame the arteries from a distance?

    Healthy fat stores energy safely and releases it on cue. Sick fat does neither well. Overfilled fat cells leak fatty acids into the blood, resist insulin’s instruction to hold on to them, and call in immune cells that turn a storage depot into a low-grade wound that never heals. Immunologists call this chronic metabolic inflammation, or metaflammation: the immune system and the metabolism stuck in a loop that feeds obesity, diabetes and the diseases that follow them.

    That inflammation reaches the arteries two ways. From the inside, through the blood: inflammatory signals, sticky lipoproteins and a clot-prone state carried to every vessel wall. And from the outside, from fat that sits directly on the heart. Surgeons who took paired samples from 42 patients having bypass surgery found that the fat on the surface of the heart made more of the inflammatory messengers interleukin-1 beta, interleukin-6, MCP-1 and TNF-alpha than the fat under the skin of the same patients. That outside-in injury is the subject of how fat around the heart injures it.

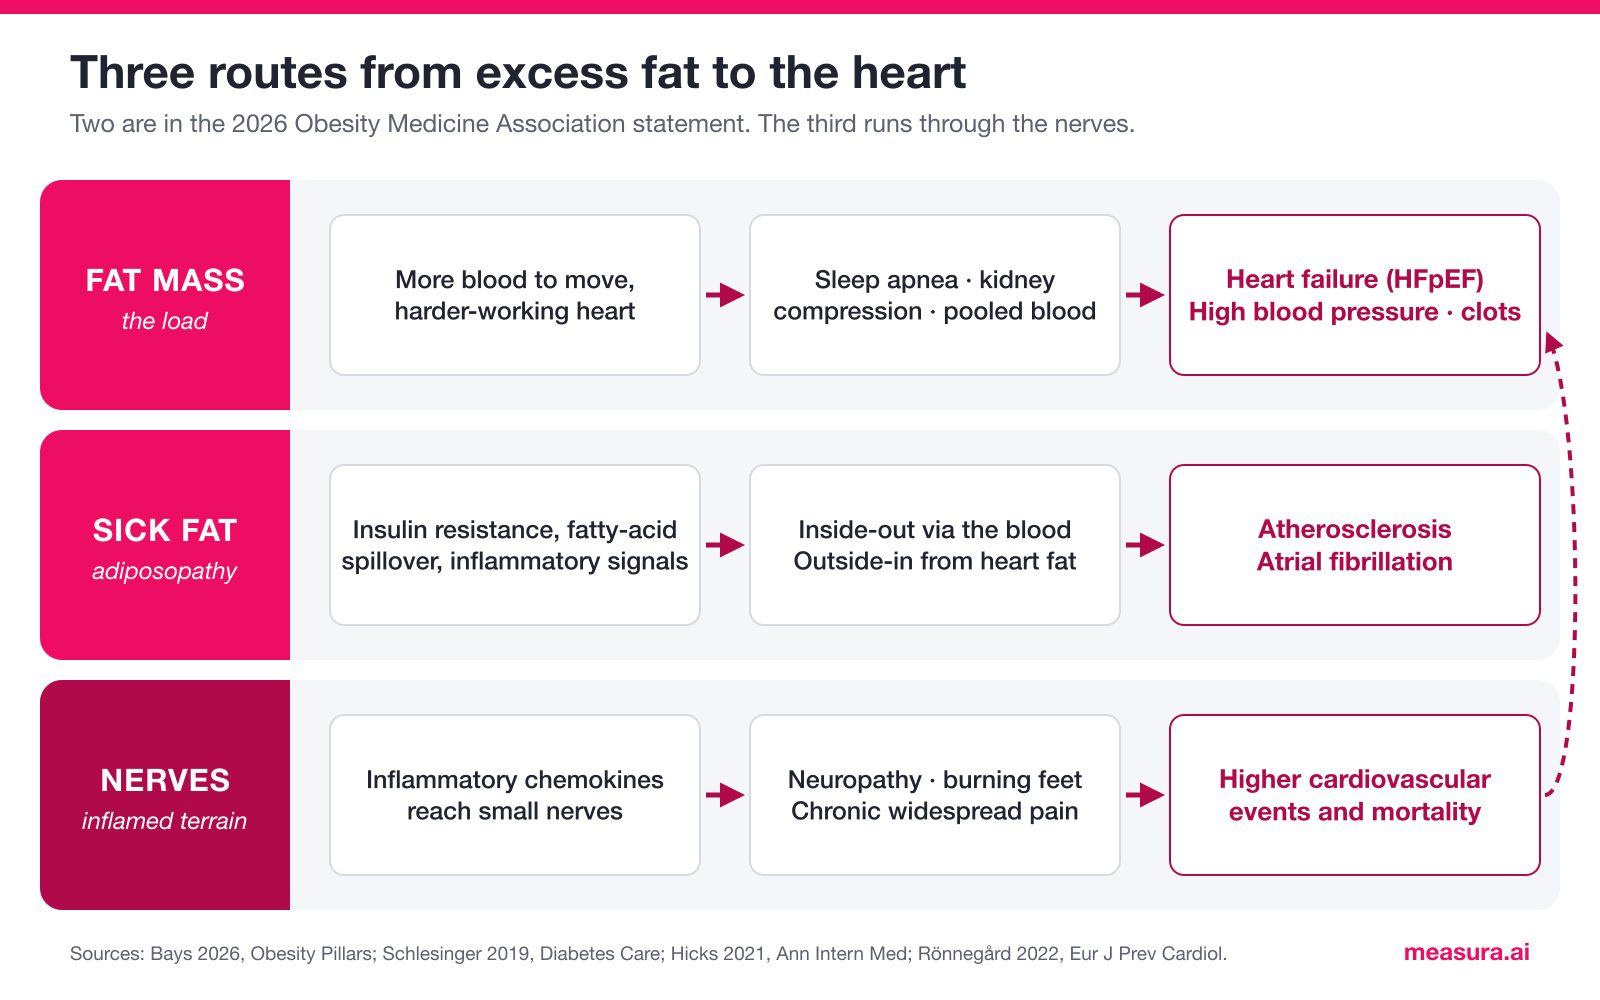
    Diagram of three routes from excess fat to heart disease. Fat mass, the load, runs through more blood to move, sleep apnea, kidney compression and pooled blood to heart failure with preserved ejection fraction, high blood pressure and clots. Sick fat, or adiposopathy, runs through insulin resistance, fatty-acid spillover and inflammatory signals, acting inside-out through the blood and outside-in from fat on the heart, to atherosclerosis and atrial fibrillation. A third route through the nerves runs from inflammatory chemokines to neuropathy and chronic widespread pain, which are linked to higher cardiovascular events and mortality.
    Two pathways from excess fat to heart disease, plus the branch most heart diagrams leave out: the same inflammation reaches the nerves, and nerve damage and chronic pain then predict heart events in their own right. Original Measura illustration.

    Where do nerves and chronic pain fit in?

    This is the branch the standard drawings leave out. The same inflamed terrain that hardens arteries damages small nerves. In a German cohort of 513 adults aged 62 to 81 followed for about six and a half years, obesity raised the odds of developing a sensory neuropathy in the feet by about three and a half times compared with normal weight, and each extra 5 cm of waist added 22% to the odds, with or without diabetes. Part of that effect ran through inflammatory chemokines measured in the blood. In a US study of adults in a weight management program and lean volunteers, neuropathy turned up in 3.8% of lean adults but in 11.1% of adults with obesity whose blood sugar was still normal, and waist size was one of the factors tied to it.

    The arrow then turns back toward the heart. In a US national sample of 7,116 adults aged 40 and older, reduced sensation in the feet was tied to higher death rates over 13 years, even in people without diabetes. In the UK Biobank, chronic widespread pain carried a 48% higher risk of heart attack, stroke, heart failure or cardiovascular death after adjusting for the usual risk factors, and the share of cardiovascular disease attributable to chronic pain was comparable with the share attributable to diabetes. Burning feet and an aching body are not a separate file from the heart. They are often the same file, opened at a different page. What a high-sensitivity CRP number says covers the blood marker that sits in the middle of all three branches.

    Why is BMI the wrong ruler for heart risk?

    BMI divides weight by height squared. It cannot tell muscle from fat, belly fat from hip fat, or quiet fat from inflamed fat. A working group of the International Atherosclerosis Society argued in 2020 that waist circumference adds information BMI misses at every BMI level, and that it should be treated as a vital sign, measured at every visit like blood pressure.

    The population numbers show how little the scale explains. Under 12.2% of US adults met optimal metabolic health on NHANES 2009–2016 criteria, and among adults with obesity the figure was 0.5%. Less than a third of normal-weight adults qualified either. By 2017–2018, on tighter cardiometabolic criteria, it was under 7%, with the steepest decline in adiposity. That is the general population, not a clinic’s, and it means most people with a “normal” BMI still carry some of the sick-fat story. How to measure visceral fat walks through the measurements that do see it.

    What does “treat obesity first” mean for your heart?

    The OMA statement’s central instruction is a change in order. Instead of treating each downstream number separately, one pill for pressure, one for sugar, one for lipids, the statement says to treat the excess and dysfunctional fat that drives all of them, and calls this “treat obesity first”. Adding one more hose for every new fire while the warehouse keeps burning is how the system has worked for decades.

    There is now outcome evidence that treating the fat changes the heart. In the SELECT trial, 17,604 adults aged 45 and older with existing cardiovascular disease, a BMI of 27 or more and no diabetes received weekly semaglutide 2.4 mg or placebo. Over a mean of 39.8 months, heart attack, stroke or cardiovascular death occurred in 6.5% on semaglutide and 8.0% on placebo, a 20% relative reduction. GLP-1 medicines may be part of your solution, chosen for specific problems after a full evaluation. They are a tool inside a plan, not the plan.

    The plan itself is mostly what happens outside the exam room. Acellular carbohydrates (flour and sugar stripped of the cell walls that slow their absorption) spike insulin, and high insulin keeps fat locked in storage. Industrial seed oils load cell membranes with oxidation-prone fats. Muscle is the largest sink for blood sugar, so losing weight without lifting anything trades fat for sarcopenic wasting and leaves the engine smaller. Short sleep raises the appetite hormones and worsens insulin resistance by morning. And the cheapest calories on the shelf are the ones engineered to be overeaten, so what a neighborhood sells and what a paycheck covers shape a waistline long before willpower enters the picture.

    Dr. Padda spent years as a strict vegetarian defending the dietary guidelines he now takes apart, until a bite of beef on a bun at Gates Bar-B-Q in Kansas City ended it. He changed his mind because the physiology told him to. That is the standard for any plan built on these measurements: when the numbers move the wrong way, the plan changes, not the patient’s character.

    What can be measured, and what does Measura measure?

    Measura does not image the heart. When a result calls for an echocardiogram, a CT or a cardiology visit, that is what the report says. For the risk score your doctor already uses and what it leaves out, see ASCVD risk: what the calculator misses. Physicians building this into practice will find the workflow in the adiposopathy screening protocol and the evidence on neuropathy and chronic pain as cardiovascular risk markers.

    The so-what is simple. Your weight is one number. Your heart risk lives in a dozen others, most of which can be measured this month and re-measured in three. Knowing which kind of fat problem you have, the load, the fire or both, tells you what to fix first and lets you see whether it is working.

    If you have chest pain, pressure, sudden shortness of breath or new weakness on one side, call 911. Measura testing is for planning, not emergencies.

    Frequently asked questions

    Can a thin person have sick fat?

    Yes. In NHANES 2009–2016, less than a third of normal-weight US adults met optimal metabolic health. Fat stored around the organs and inside the liver can be inflamed while total weight looks fine, which is why waist, body composition and insulin tell you more than BMI.

    Does losing weight calm sick fat, or just make it smaller?

    It calms it. In a 52-week trial in adults with obesity-related heart failure, people who lost an average of 13.3% of their weight on semaglutide saw C-reactive protein, an inflammation marker, fall 43.5%, against 7.3% on placebo. Inflammation followed the fat down.

    Is the “obesity paradox” a reason not to worry about weight?

    No. The paradox mostly disappears when fat is judged by how it functions rather than how much there is. A heavier person with healthy fat and a lighter person with inflamed visceral fat are not the same risk, and only measurement tells them apart.

    Measure both kinds of fat risk

    Ask for body composition, vascular and autonomic testing, and the inflammation and insulin markers that show whether your fat is carrying weight or making trouble.

    4477 Woodson Rd, Suite 201, St. Louis, MO 63134. Monday to Friday, 9:00 a.m. to 5:00 p.m. Please do not send symptoms, diagnoses or images through a web form — a website form is not a secure medical channel. Send your name and number and we will call you back.

    References

    • Bays, H. E., Varney, C., Alexander, L., Ng, J., Tondt, J., Weber, C., et al. (2026). Obesity and Cardiovascular Disease: An Obesity Medicine Association (OMA) Clinical Practice Statement (CPS) 2026. Obesity Pillars, 20, 100283. https://doi.org/10.1016/j.obpill.2026.100283 (PMID 42729919)
    • Bays, H. E. (2011). Adiposopathy is “sick fat” a cardiovascular disease?. Journal of the American College of Cardiology, 57(25), 2461-2473. https://doi.org/10.1016/j.jacc.2011.02.038 (PMID 21679848)
    • Hotamisligil, G. S. (2017). Inflammation, metaflammation and immunometabolic disorders. Nature, 542(7640), 177-185. https://doi.org/10.1038/nature21363 (PMID 28179656)
    • Mazurek, T., Zhang, L., Zalewski, A., Mannion, J. D., Diehl, J. T., Arafat, H., et al. (2003). Human epicardial adipose tissue is a source of inflammatory mediators. Circulation, 108(20), 2460-2466. https://doi.org/10.1161/01.CIR.0000099542.57313.C5 (PMID 14581396)
    • Schlesinger, S., Herder, C., Kannenberg, J. M., Huth, C., Carstensen-Kirberg, M., Rathmann, W., et al. (2019). General and Abdominal Obesity and Incident Distal Sensorimotor Polyneuropathy: Insights Into Inflammatory Biomarkers as Potential Mediators in the KORA F4/FF4 Cohort. Diabetes Care, 42(2), 240-247. https://doi.org/10.2337/dc18-1842 (PMID 30523031)
    • Callaghan, B. C., Xia, R., Reynolds, E., Banerjee, M., Rothberg, A. E., Burant, C. F., et al. (2016). Association Between Metabolic Syndrome Components and Polyneuropathy in an Obese Population. JAMA Neurology, 73(12), 1468-1476. https://doi.org/10.1001/jamaneurol.2016.3745 (PMID 27802497)
    • Hicks, C. W., Wang, D., Matsushita, K., Windham, B. G., & Selvin, E. (2021). Peripheral Neuropathy and All-Cause and Cardiovascular Mortality in U.S. Adults : A Prospective Cohort Study. Annals of Internal Medicine, 174(2), 167-174. https://doi.org/10.7326/M20-1340 (PMID 33284680)
    • Rönnegård, A.-S., Nowak, C., Äng, B., & Ärnlöv, J. (2022). The association between short-term, chronic localized and chronic widespread pain and risk for cardiovascular disease in the UK Biobank. European Journal of Preventive Cardiology, 29(15), 1994-2002. https://doi.org/10.1093/eurjpc/zwac127 (PMID 35727954)
    • Ross, R., Neeland, I. J., Yamashita, S., Shai, I., Seidell, J., Magni, P., et al. (2020). Waist circumference as a vital sign in clinical practice: a Consensus Statement from the IAS and ICCR Working Group on Visceral Obesity. Nature Reviews Endocrinology, 16(3), 177-189. https://doi.org/10.1038/s41574-019-0310-7 (PMID 32020062)
    • Araújo, J., Cai, J., & Stevens, J. (2019). Prevalence of Optimal Metabolic Health in American Adults: National Health and Nutrition Examination Survey 2009-2016. Metabolic Syndrome and Related Disorders, 17(1), 46-52. https://doi.org/10.1089/met.2018.0105 (PMID 30484738)
    • O’Hearn, M., Lauren, B. N., Wong, J. B., Kim, D. D., & Mozaffarian, D. (2022). Trends and Disparities in Cardiometabolic Health Among U.S. Adults, 1999-2018. Journal of the American College of Cardiology, 80(2), 138-151. https://doi.org/10.1016/j.jacc.2022.04.046 (PMID 35798448)
    • Lincoff, A. M., Brown-Frandsen, K., Colhoun, H. M., Deanfield, J., Emerson, S. S., Esbjerg, S., et al. (2023). Semaglutide and Cardiovascular Outcomes in Obesity without Diabetes. New England Journal of Medicine, 389(24), 2221-2232. https://doi.org/10.1056/NEJMoa2307563 (PMID 37952131)

    Related reading

  • Close-up of tailor's hands measuring a person's waist with a yellow tape.

    Does Obesity Cause Cancer? What Your Metabolic Numbers Add

    Does Obesity Cause Cancer? What Your Metabolic Numbers Add

    Yes, for a growing list of cancers: higher BMI is tied to greater risk of 19 cancer types, and the risk travels through what excess fat does to blood sugar, insulin and inflammation.

    About four in ten US cancers trace to factors people can change, and excess weight ranks second. The deeper driver is metabolic, and most of it goes unmeasured at a routine visit.

    Does obesity cause cancer? For a growing list of cancers the evidence now says it does, and the number on the scale is the least interesting part of the answer: the risk travels through what excess fat does to blood sugar, insulin and inflammation, the metabolic damage a routine checkup rarely measures.

    How much cancer is tied to things that can change

    American Cancer Society researchers estimated that in 2019, 40.0% of new cancers in US adults aged 30 and older, 713,340 of 1,781,649 cases outside common skin cancers, and 44.0% of cancer deaths, 262,120 of 595,737, were attributable to risk factors that can potentially be changed. Cigarette smoking led, at 19.3% of cases and 28.5% of deaths. Excess body weight came second, at 7.6% of cases and 7.3% of deaths, ahead of alcohol at 5.4% and 4.1%.

    Treat that 7.6% as a floor for metabolic harm, not a ceiling. The analysis counted excess body weight. High blood sugar, insulin resistance and metabolic syndrome were not on its list of evaluated risk factors, so a person of ordinary weight whose metabolism is failing added nothing to that share. The headline undercounts exactly the person a scale reassures, and the metabolic part of the story has to be read from other studies.

    The list of weight-linked cancers keeps growing

    In 2024, two cancer epidemiologists writing in The Lancet Regional Health – Europe asked the question directly: is obesity a cause of all cancer types? A 2026 systematic review in Nature Metabolism, with one of those two on its author team, gave the most complete answer so far. It pooled 226 articles covering 1.5 million cancer diagnoses from prospective studies of 25 cancer types and found higher BMI tied to greater risk of 19 cancers and lower risk of 3. Leukemia, non-Hodgkin lymphoma, bladder cancer and glioma were added compared with earlier consensus reports. Waist circumference behaved much like BMI, and genetic studies were generally consistent with the observational findings. Not every cancer, then, but far more than most people assume. Liver cancer is on that list, and the first warning is often a scarring score most patients never see, explained in what a fibrosis score says about a fatty liver.

    Metabolic syndrome carries its own risk

    Metabolic syndrome is a cluster of findings: a large waist, high blood pressure, high blood sugar, high triglycerides and low HDL cholesterol. A 2024 meta-analysis of 31 prospective cohort studies linked it to higher risk of five digestive cancers: colorectal (relative risk 1.13), esophageal (1.17), pancreatic (1.25), gallbladder (1.37) and liver (1.46). Stomach cancer was the exception. Among combinations of those findings, obesity with high blood pressure and high blood sugar had the strongest link to colorectal cancer, 1.54 in men and 1.27 in women. Genetic studies within the same paper, a way of separating cause from coincidence, supported waist-to-hip ratio, BMI and HbA1c, the three-month blood sugar average, as causes of colorectal cancer.

    This evidence is observational and genetic, not randomized, because nobody can assign people to decades of high insulin and wait for tumors; that is exactly why the mechanism carries weight. Why would metabolism feed a tumor? A 2026 review published alongside the meta-analysis names three routes: sex hormones, hyperinsulinemia and chronic inflammation. Insulin is a growth signal. When cells resist it, the pancreas pushes out more, and every tissue that listens to insulin keeps hearing an instruction to grow. Inflamed fat tissue adds a steady stream of alarm chemicals, the metaflammation that keeps repair switched on long after anything needs repairing. Two biological engines, then, and one fuel line. The third driver sits outside the body. A food supply engineered around acellular carbohydrates and industrial seed oils, much of it grown from subsidized commodity crops, keeps both engines fed meal after meal, and then the same system treats the tumor as bad luck.

    Colorectal cancer is arriving younger

    Colorectal cancer in adults under 50 has been rising since the 1990s, and a 2025 review in Nature Reviews Endocrinology described it as an emerging disease of metabolic dysregulation, climbing alongside obesity and type 2 diabetes in young people. In a 2026 meta-analysis of eleven cohort studies, overweight or obesity carried 1.59 times the odds of early-onset colorectal cancer, and obesity alone 1.81. Among 357 Australian adults referred for colonoscopy, where waist and weight told part of the story, 41.7% had metabolic syndrome, and in those over 40 with a BMI of 25 or more, the adjusted odds were 2.26 for any polyp and 2.64 for an adenoma, the type of polyp that can turn into cancer.

    Weight is not the whole explanation, and that matters for anyone who is not heavy. Australian modeling published in 2026 estimated that obesity in adolescence accounts for a growing but small share of early-onset colorectal cancers, rising from 2% to 6% in men, and judged it unlikely to be the main driver of the rise. Read beside the metabolic syndrome findings, that points past the scale toward blood sugar, insulin and inflammation. If you are young, of ordinary weight and told your risk is low because you are not heavy, that reassurance rests on the wrong number. The same trap catches the normal-BMI South Asian or East Asian adult who is skinny fat, thin outside and metabolically inflamed and insulin resistant inside.

    Risk is not fixed at the weight you once were

    In a population cohort of 800,024 people whose BMI was measured at pre-military evaluations in late adolescence and again in adulthood, those who went from a normal weight to a high one had 1.31 times the risk of obesity-related cancers, and those who stayed heavy had 1.47 times. People who were heavy as teenagers but reached a normal adult weight showed no clear excess, with a hazard ratio of 1.01. Each 5% of weight gained raised the hazard by 3%, and the same held for cancers diagnosed before 50. The trajectory, not the starting point, carried the risk, and a trajectory is something you can track and still change.

    Metabolic health, meanwhile, has become the exception. Fewer than 12.2% of US adults qualified as optimally metabolically healthy in NHANES data from 2009 through 2016, and once stricter criteria arrived after 2021 the share fell below 7%. A normal weight does not settle the question. Unmeasured is unmanaged. For older adults with high blood pressure, a waist measure adjusted for weight has been tested against stroke, as covered in waist index screening for stroke.

    What a checkup covers, and what measurement adds

    Cancer screening itself, such as colonoscopy and mammography, is ordered by your physician and done elsewhere. A standard checkup records weight and blood pressure and usually checks glucose, A1c and cholesterol. What it tends to leave out is fasting insulin, which climbs for years while glucose still looks normal, and any measure of how much of your weight is fat and how much is muscle.

    Measura [Cardiometabolic and Autonomic Health Analysis] measures; it does not screen for cancer, diagnose it or treat it, and results go to your physician.

    Questions worth bringing to your next visit: Am I due for colorectal cancer screening, given my age and family history? What is my fasting insulin, as a number? Do I meet the definition of metabolic syndrome? More prompts are in questions worth asking your doctor, and the background is in insulin resistance and metabolic health.

    Frequently asked questions

    Does obesity cause cancer, or is it only linked to it?

    For many cancers the evidence points toward cause. In a 2026 review of prospective studies, higher BMI was tied to 19 cancers, and genetic studies were generally consistent with those findings, which argues against coincidence. Excess fat acts through insulin, inflammation and hormones, so the metabolic picture matters as much as the scale. Where that fat sits is explained in how to measure visceral fat.

    Can my cancer risk be raised at a normal weight?

    Metabolic syndrome carried its own link to colorectal, liver and pancreatic cancer, and its parts, such as high blood sugar, high triglycerides and low HDL cholesterol, can appear at an ordinary weight. Weight alone does not rule out the metabolic side. What a normal A1c can hide is explained in fasting insulin test: what a normal A1c can hide.

    Does losing weight lower cancer risk?

    Trials that follow weight loss all the way to cancer diagnoses are rare, because cancer takes years to appear. In a large cohort, people who were heavy as teenagers but reached a normal adult weight showed no clear excess risk, while each 5% of weight gained raised risk by 3%. Keeping lost weight from returning is covered in how to maintain weight loss.

    Can Measura test me for cancer?

    Measura does not screen for, diagnose or treat cancer. Colonoscopy, mammography and other cancer screening are ordered by your physician and done elsewhere. Measura measures the metabolic terrain, including insulin, inflammation and body composition, and sends those results to your physician. How those numbers can be tracked as they change is described in how to lower insulin resistance.

    Why is colorectal cancer rising in younger adults?

    Nobody has a complete answer yet. Overweight and obesity raise the odds of colorectal cancer before 50, but modeling suggests adolescent obesity explains only a small share of the rise, so researchers are looking at metabolic dysregulation, diet and early-life exposures together. One piece of that terrain is discussed in does sugar cause inflammation.

    Measure the metabolic side of your risk

    Ask to have your fasting insulin, inflammation markers and body composition measured, so your physician can see the metabolic terrain that weight alone does not show.

    4477 Woodson Rd, Suite 201, St. Louis, MO 63134. Monday to Friday, 9:00 a.m. to 5:00 p.m. Please do not send symptoms, diagnoses or images through a web form — a website form is not a secure medical channel. Send your name and number and we will call you back.

    References

    • Islami, F., Marlow, E. C., Thomson, B., McCullough, M. L., Rumgay, H., Gapstur, S. M., Patel, A. V., Soerjomataram, I., & Jemal, A. (2024). Proportion and number of cancer cases and deaths attributable to potentially modifiable risk factors in the United States, 2019. CA: A Cancer Journal for Clinicians, 74(5), 405-432. https://doi.org/10.3322/caac.21858
    • Gunter, M. J., & Berrington de Gonzalez, A. (2024). Is obesity a cause of all cancer types? The Lancet Regional Health – Europe, 46, 101110. https://doi.org/10.1016/j.lanepe.2024.101110
    • Watts, E. L., Gonzalez-Feliciano, A., Gunter, M. J., Chatterjee, N., & Moore, S. C. (2026). Adiposity and cancer: systematic review and meta-analysis. Nature Metabolism, 8(6), 1426-1439. https://doi.org/10.1038/s42255-026-01542-8
    • Watts, E. L., Gonzalez-Feliciano, A., Gunter, M. J., Chatterjee, N., & Moore, S. C. (2026). Adiposity and cancer: epidemiology, mechanisms and future perspectives. Nature Metabolism, 8(6), 1266-1281. https://doi.org/10.1038/s42255-026-01529-5
    • Zhan, Z. Q., Chen, Y. Z., Huang, Z. M., Luo, Y. H., Zeng, J. J., Wang, Y., Tan, J., Chen, Y. X., & Fang, J. Y. (2024). Metabolic syndrome, its components, and gastrointestinal cancer risk: a meta-analysis of 31 prospective cohorts and Mendelian randomization study. Journal of Gastroenterology and Hepatology, 39(4), 630-641. https://doi.org/10.1111/jgh.16477
    • Du, M., Drew, D. A., Goncalves, M. D., Cao, Y., & Chan, A. T. (2025). Early-onset colorectal cancer as an emerging disease of metabolic dysregulation. Nature Reviews Endocrinology, 21(11), 686-702. https://doi.org/10.1038/s41574-025-01159-z
    • Wang, H., Wu, C., Zhou, S., Shi, Y., Cheng, L., Cao, H., Zhang, Y., & Gao, S. (2026). Body mass index and early-onset colorectal cancer risk: a systematic review and cohort-based meta-analysis. Scandinavian Journal of Gastroenterology, 61(4), 383-396. https://doi.org/10.1080/00365521.2026.2615397
    • Kumar, R., Brown, A., Okano, S., Simms, L., Lord, A., O’Sullivan, T., Hartel, G., & Radford-Smith, G. L. (2024). Overweight and obesity are associated with colorectal neoplasia in an Australian outpatient population. Scientific Reports, 14(1), 23501. https://doi.org/10.1038/s41598-024-74042-y
    • Min, J., Jenkins, M. A., & Meyers, A. L. (2026). Early-onset colorectal cancer burden attributable to early-life obesity from 2000 to 2020 with projections to 2040. Cancer Epidemiology, 105, 103219. https://doi.org/10.1016/j.canep.2026.103219
    • Bendor, C. D., Bardugo, A., Tsur, A. M., Derazne, E., Shemesh, I. I., Bourvine, L., et al. (2026). Adolescent to adulthood weight trajectories and the risk of obesity-related cancers, overall and early-onset: a population-based cohort study. EClinicalMedicine, 91, 103711. https://doi.org/10.1016/j.eclinm.2025.103711

    Related reading

  • Adult slicing cucumber on a wooden board beside fresh vegetables.

    Nutrition Before Surgery: What to Have Measured While You Wait

    Nutrition Before Surgery: What to Have Measured While You Wait

    Nutrition before surgery shapes how you heal: malnourished spine surgery patients had 2.10 times the odds of wound complications and 2.77 times the odds of sepsis. The standard preoperative workup checks your heart and lungs for anesthesia, not the materials you need to heal.

    An elective operation comes with a date. The weeks before it are the only stretch when your muscle, nutrients and energy use can be measured, and those numbers shape how you heal.

    Nutrition before surgery gets treated as a dietitian’s problem, reserved for frail, underweight patients in hospital beds. That framing is wrong: you close a surgical wound, fight infection and rebuild strength with the protein, muscle and micronutrients you carry through the door, and the standard preoperative workup is built to confirm your heart and lungs can handle anesthesia, not to check whether you brought the materials to heal.

    What poor nutrition does to recovery

    The clearest numbers come from spine surgery. A 2026 review pooled 37 studies that together included 16,987 malnourished patients. Compared with well-nourished patients, those who were malnourished had 1.79 times the odds of surgical complications, 2.10 times the odds of wound complications, 2.77 times the odds of sepsis and 4.05 times the odds of dying. Their odds of delirium were 3.95 times higher and their odds of a prolonged hospital stay 3.46 times higher. If a spine operation is on your calendar, the broader question of what counts as success is covered in lumbar fusion success rate: what to measure before you decide.

    Older adults having bone and joint operations show the same pattern. Across 11 studies with 201,338 older orthopedic surgery patients, malnutrition picked up by a screening tool went with 1.65 times the risk of complications and 2.17 times the risk of death after surgery. In hip and knee replacement, a low score on the Geriatric Nutritional Risk Index went with 1.59 times the odds of a surgical site infection across 221,810 patients.

    Frailty multiplies it. In 1,361 adults aged 65 or older having elective surgery, the people who were both malnourished and frail before the operation had 5.36 times the risk of dying within a year and 4.83 times the odds of major complications, compared with people who were neither.

    Malnourished does not have to mean thin

    Many people picture malnutrition as someone visibly wasting away. The measurements say otherwise. A 2026 review of knee replacement studies covering more than 93,000 patients found that people with sarcopenia, meaning too little muscle, had more complications, falls, fractures and repeat operations, and regained knee motion and walking speed more slowly, particularly when low muscle came together with obesity. A larger body can hold a small muscle reserve, and a bathroom scale cannot tell the difference. The same gap between weight and nourishment is explained in can you be overweight and malnourished.

    Two biological forces drain those stores at once, and they feed each other. Metaflammation, the low-grade inflammation that travels with excess body fat and with chronic pain, keeps pulling on protein. Pain cuts how much you move, so muscle wastes in exactly the months a joint or spine is failing, and a smaller muscle reserve leaves less to draw on when the operation adds its own stress. The third force is the system. Surgical scheduling runs on a date and a clearance form, and the clearance form has no line for muscle, nutrients or energy use. Nobody fills in a box that does not exist. Clinicians screening for this pattern have a separate guide in screening for malnutrition when a patient has obesity.

    Why one blood number is not enough

    Blood albumin, a protein made by the liver, is the shortcut the system reaches for, because it is already on the panel. It does carry a signal. Across 40 studies with 477,701 patients, low albumin before surgery went with 2.88 times the odds of lung complications and death after general anesthesia, and 4.03 times in orthopedic surgery. Yet the reviewers of the orthopedic studies pointed out that single blood values such as albumin forecast complications with limited precision. A normal albumin does not prove you are well nourished, and a low one does not say what is missing. That is why screening tools combine several measures, and why muscle, nutrients and energy use are worth measuring directly.

    Why measuring first changes the plan

    Some of this risk responds to the weeks before the date. A 2024 Cochrane review of 16 randomized trials with 2,164 people having digestive surgery found that standard oral nutrition drinks made little difference to complications when well-nourished and malnourished patients were pooled together. In the patients who were already malnourished or losing weight, the same drinks probably reduced infections, with a risk ratio of 0.58. A separate 2024 analysis of 12 trials with 1,201 patients having surgery for digestive cancers found that nutrition supplements taken before surgery lowered infectious complications, with an odds ratio of 0.63, and raised albumin, although hospital stays were no shorter. Both reviews studied digestive surgery, so the metabolically complex patient headed for a joint or spine operation is barely represented. Trials are built that way to get a clean answer; the physiology still applies to you, and your own numbers are how you find out whether it does.

    This is the part most patients never hear. The benefit showed up in the people who were actually short. So the first question is not what to eat before surgery. It is whether you are short at all, and on what, and nobody can answer that from your weight. Get the answer while there is still time on the calendar to act on it, and put it in front of the surgeon and physician who will decide what to do with it. Many people facing joint surgery also carry a metabolic driver in those joints, described for physicians in metabolic osteoarthritis screening.

    What a routine preoperative visit checks, and what it misses

    A typical preoperative evaluation reviews your heart and lungs, your medications and a basic blood panel, and it records your weight. What it usually leaves out is any measurement of muscle, a look at nutrient status beyond that basic panel, and a number for how much energy your body actually burns.

    Measura [Cardiometabolic and Autonomic Health Analysis] measures and reports to your physician; it does not operate, prescribe or clear anyone for surgery. Three of its measurements fit the weeks before an elective procedure:

    • Bioimpedance body composition estimates muscle, fat and water separately while you stand on a platform for a couple of minutes, so a low muscle reserve shows up even when your weight looks ample. The difference is laid out in body composition, not BMI.
    • Laboratory panels can include nutrient markers such as vitamin B12, zinc and red blood cell magnesium, inflammatory markers such as C-reactive protein and ferritin, and blood sugar alongside insulin. Albumin and vitamin D come from the blood work your physician orders.
    • Indirect calorimetry measures your resting energy use from the air you breathe in and out, which gives any nutrition plan a real starting number instead of an estimate.

    Repeated under the same conditions before the date, these turn a vague instruction to eat well into numbers that can be checked. Unmeasured is unmanaged, and an elective operation is the rare situation where you know exactly how long you have to measure.

    Questions to bring to your surgeon or physician

    • Has my nutrition been screened, and with which tool?
    • Is my muscle mass known, or only my weight?
    • Would my albumin, vitamin D or B12 change anything about timing or preparation?
    • If my results show a shortfall, is there time to address it before the date, and who will manage that?
    • Who will look at my results again before the operation?

    More prompts are collected in questions worth asking your doctor.

    Frequently asked questions

    Why does nutrition before surgery matter if I feel fine?

    Feeling fine and having reserves are different things. Healing draws on protein, muscle and micronutrients you already carry, and in older orthopedic patients malnutrition found by a screening tool went with higher risks of complications and death. Most shortfalls cause no symptoms until the body is stressed. Whether testing makes sense for you is covered in who should have cardiometabolic testing.

    Can I be malnourished if I am overweight?

    Weight measures stored fuel, not muscle or nutrients. In knee replacement studies, people with too little muscle had more complications and slower recovery, especially when low muscle came with obesity. A body composition test separates muscle from fat so the difference is visible. The idea is explained further in body composition is not the same as weight.

    Is a normal albumin level enough to rule out malnutrition?

    A normal albumin is reassuring but incomplete. Low albumin before surgery is linked to lung complications and death, yet single blood values forecast complications with limited precision, and albumin says nothing about muscle mass or specific nutrients. Your physician reads it alongside other measurements. Why one number cannot settle the question is covered in what a test result can and cannot tell you.

    When should nutrition testing happen before an elective operation?

    Earlier is more useful, because a shortfall found the week before surgery leaves little room to act on it. Testing as soon as a date is being discussed gives your surgeon and physician time to decide whether anything should change and to repeat a measurement. Practical details are in what happens before your appointment.

    Does Measura decide whether I am ready for surgery?

    Measura measures and reports; it does not decide. Body composition, laboratory panels and resting metabolic rate go to your physician, who interprets them with your history and works with your surgeon on timing and preparation. Measura performs no surgery and prescribes no nutrition therapy. The full list of measurements is in what Measura actually measures.

    Get measured before your surgery date

    Ask to have your body composition, nutrient laboratory panels and resting metabolic rate measured, so your surgeon and physician can plan around numbers instead of your weight.

    4477 Woodson Rd, Suite 201, St. Louis, MO 63134. Monday to Friday, 9:00 a.m. to 5:00 p.m. Please do not send symptoms, diagnoses or images through a web form — a website form is not a secure medical channel. Send your name and number and we will call you back.

    References

    • Ashraf, A., Kaghazchi, A., Jelkin, G., Karnati, J., Lunasco, L., Abid, S., et al. (2026). Malnutrition and adverse outcomes after spine surgery: a systematic review and meta-analysis. The Spine Journal, 26(10), 2045-2074. https://doi.org/10.1016/j.spinee.2026.06.015
    • Li, D., Shi, J., Zheng, J., & Hu, Y. (2026). Nutritional screening tools as predictors of surgical outcomes in geriatric orthopedic patients: a meta-analysis. Aging Clinical and Experimental Research, 38(1), 51. https://doi.org/10.1007/s40520-025-03306-y
    • Du, M., Liu, T., Liu, Y., Guo, J., Ma, X., Zhai, L., et al. (2026). Preoperative GNRI and surgical site infection risk after total joint arthroplasty: A systematic review and meta-analysis. Biomolecules & Biomedicine, 26(10), 1706-1719. https://doi.org/10.17305/bb.2026.13414
    • Dong, L., Hu, B., Wen, F., Shi, S., Liang, Y., Qin, L., et al. (2026). Association between malnutrition and frailty and postoperative mortality in older surgical patients. Clinical Nutrition, 63, 106695. https://doi.org/10.1016/j.clnu.2026.106695
    • Za, P., Minelli, M., Esposito, C., Longobardi, V., Vasta, S., Calafiore, G., & Della Rocca, F. (2026). Sarcopenia and Postoperative Outcomes Following Total Knee Arthroplasty: A Systematic Review of Observational Studies. Journal of Clinical Medicine, 15(14). https://doi.org/10.3390/jcm15145523
    • Wang, X., Tang, H., Zheng, M., & Xu, F. (2026). Hypoalbuminaemia contributes to postoperative pulmonary complications and mortality: a systematic review and meta-analysis. BMC Anesthesiology, 26(1). https://doi.org/10.1186/s12871-025-03329-y
    • Sowerbutts, A. M., Burden, S., Sremanakova, J., French, C., Knight, S. R., & Harrison, E. M. (2024). Preoperative nutrition therapy in people undergoing gastrointestinal surgery. Cochrane Database of Systematic Reviews, 4, CD008879. https://doi.org/10.1002/14651858.CD008879.pub3
    • Zou, Q., Yin, Z., Ding, L., Ruan, J., Zhao, G., Wang, X., et al. (2024). Effect of preoperative oral nutritional supplements on clinical outcomes in patients undergoing surgery for gastrointestinal cancer: A systematic review and meta-analysis. Medicine, 103(39), e39844. https://doi.org/10.1097/MD.0000000000039844

    Related reading

  • Plate of eggs, avocado and vegetables beside a cup of coffee.

    Ketones as Brain Fuel: The Entrance Insulin Resistance Cannot Close

    Ketones as Brain Fuel: The Entrance Insulin Resistance Cannot Close

    Ketones fuel the brain without insulin: they enter nerve cells through carriers that depend on neither insulin nor the GLUT4 glucose transporter. When insulin resistance closes part of the glucose supply to the memory circuits, ketones still get in.

    The memory circuits partly depend on an insulin-sensitive glucose door. Ketones use a different entrance, and that single difference explains why researchers keep testing them in the insulin-resistant brain.

    An insulin-resistant brain is not out of fuel; it is locked out of one fuel while the other sits in the bloodstream unused. Using ketones for brain fuel matters because they walk in through an entrance insulin does not guard, while in the memory circuits the glucose doors partly answer to insulin. That is plumbing, not diet-book language, and the insulin side of it shows up on fasting laboratory panels. When insulin signaling fails, that difference decides whether a nerve cell is starving or simply switching fuels. Measura [Cardiometabolic and Autonomic Health Analysis] does not prescribe diets or supply ketones; it measures the insulin and fuel picture that makes the question relevant to you.

    Two fuels, two ways in

    Most of the time the brain burns glucose. Transporter proteins carry it across the blood-brain barrier and into cells, and most of that traffic does not need insulin. The exception matters. Nerve cells in the hippocampus, the structure that turns experience into memory, also use an insulin-responsive glucose transporter called GLUT4 when demand spikes, the way a grocery store opens extra checkout lanes at rush hour. If insulin stops working, those extra lanes stay closed exactly when the line is longest.

    Ketones, mainly beta-hydroxybutyrate and acetoacetate, are made by the liver from fat when insulin runs low: overnight, during longer fasts or with carbohydrate restriction. They enter nerve cells through a separate family of carriers that depends on neither GLUT4 nor insulin. That independence is the reason researchers began asking whether ketones could keep an insulin-resistant brain running. How normal ketosis differs from the medical emergency of ketoacidosis is explained in ketosis vs ketoacidosis.

    What happened when the insulin door was shut

    This is mouse work. In a 2024 study, researchers at the University of Rochester and Stony Brook University took thin slices of mouse hippocampus and chemically blocked GLUT4, creating a short-term version of insulin resistance in living tissue. The circuit linking two hippocampal regions, called CA3 and CA1, degraded in several ways at once. Synaptic activity fell. Long-term potentiation, the strengthening of connections that underlies learning, weakened. Signals traveled along nerve fibers less reliably, and groups of cells fell out of step with one another.

    Then the researchers added D-beta-hydroxybutyrate, the main ketone the body makes. It did not restore everything, but it rescued conduction along the fibers, the synchronization between cells and long-term potentiation. The non-obvious point is where the rescue landed. Memory depends on timing, on many cells firing together within thousandths of a second, and timing is expensive. When fuel runs short, precision fails long before cells die. A brain with enough energy on paper can still lose the synchrony that learning requires.

    A slice of mouse tissue is not a person. Human trials of ketones usually isolate one diagnosis and exclude the metabolically complicated patient, so the mechanism has to carry more of the explanation here than it would in a simpler field. Why the insulin gate deserves a blood test of its own is argued in fasting insulin as an early screen.

    Human brains: glucose uptake falls, ketone uptake holds

    A research group in Sherbrooke, Quebec, measured both fuels in living brains using PET scans with two tracers, one for glucose and one for the ketone acetoacetate. In 10 people with mild Alzheimer’s disease, average age 76, compared with 29 cognitively normal adults, average age 75, gray matter took up 13% less glucose. Ketone uptake did not differ. In a second comparison of 24 healthy older adults, 20 with mild cognitive impairment and 19 with early Alzheimer’s disease, a glucose shortfall of about 7% had already appeared in one region, the cingulate gyrus, at the mild impairment stage, while ketone metabolism still matched the healthy group.

    Supply mattered as much as access. When people with mild to moderate Alzheimer’s disease took 30 g a day of a medium-chain triglyceride supplement for one month, brain ketone consumption doubled without any change in brain glucose use. In adults with mild cognitive impairment randomized to a ketogenic drink or placebo, brain ketone metabolism rose by 230% after 6 months, and several memory, language and processing-speed scores improved from baseline. The deficit in these brains is specific to glucose, and the second entrance stays open. Whether a whole diet does the same in daily life is covered in what to measure before believing keto helps Alzheimer’s.

    Brain networks in living adults, and a limit worth knowing

    The Stony Brook group had earlier asked whether fuel type changes how brain networks hold together. Using imaging datasets of 292 and 636 adults spanning young adulthood to old age, they found that network stability, the ability of brain regions to stay in sustained communication, declined with age and tracked cognitive sharpness. In younger adults scanned in an ultrahigh-field scanner, networks became less stable after glucose and more stable with ketones, whether ketosis came from a ketogenic diet or from a ketone ester drink.

    Newer work tested people closer to the question. In a 2025 randomized crossover trial of 10 adults with metabolic syndrome and 10 matched adults without it, working memory improved after a single ketone ester drink in both groups. The limit is instructive too. In a 12-week pilot in community-dwelling adults aged 65 and older who were healthy and independent, a daily ketone ester did not change exploratory measures of function or quality of life. Extra fuel appears to matter most where fuel is short, which is exactly why knowing whether your insulin system is failing comes first. The tissue evidence for that failing insulin system is traced in what brain tissue shows about insulin resistance in Alzheimer disease.

    Why the insulin entrance closes in the first place

    Three forces do most of the work, two of them biological. The first is constant insulin: a pancreas that answers every snack keeps insulin elevated, and cells exposed to a signal that never stops learn to ignore it. The second is metaflammation, the low-grade inflammatory output of overfilled visceral fat, which interferes with the same relay proteins insulin needs inside the cell. The third force is social. Food is engineered and sold to be eaten from waking to bedtime, and a day without a real fasting gap is a day the liver never makes ketones at all. The brain was built to alternate fuels; the modern schedule rarely lets it. How that plays out across the whole body is laid out in insulin resistance and metabolic health. Repeated glucose spikes damage more than the brain, starting with the lining inside every blood vessel.

    What a standard visit checks, and what can be measured

    A routine visit reports fasting glucose and sometimes hemoglobin A1c. Neither says how much insulin it took to hold glucose there, and nothing in a standard workup shows which fuel your body is burning. Measura measures; it does not treat, and results go to your physician.

    • Insulin behind the glucose. Laboratory panels can include fasting insulin alongside glucose and hemoglobin A1c. A blood ketone level, if wanted, is blood work your physician orders.
    • Which fuel you burn at rest. Indirect calorimetry measures oxygen used and carbon dioxide produced after a fast and reports a respiratory quotient, which indicates whether you are predominantly burning fat or carbohydrate. The practical side is in metabolic rate and energy.
    • A memory starting point. Cognitive assessment records attention, memory and executive function so that any later change is measured against you.

    If you take medication for diabetes or blood pressure, any change in eating that raises ketones is a conversation with your prescriber before it starts. Unmeasured is unmanaged, and the brain’s second fuel is only an option for someone who knows the first one is failing.

    Frequently asked questions

    Can the brain run entirely on ketones?

    Not entirely. Some brain cells and all red blood cells still need glucose, and the liver keeps making it even during a long fast. What ketones can do is cover a large share of the brain’s energy need, and they reach nerve cells without depending on insulin. That matters most when insulin-dependent glucose uptake is faltering, the problem described in fasting insulin screening before glucose moves.

    Is a ketone drink the same as a ketogenic diet?

    They raise the same molecules by different routes. A ketone ester or medium-chain triglyceride supplement raises blood ketones within hours while insulin and diet stay much the same, whereas a ketogenic diet lowers insulin and changes fat, muscle and liver metabolism over weeks. The brain scan studies used both approaches. How physicians weigh the options in memory complaints is covered in ketogenic therapy in mild cognitive impairment.

    Is it safe to try ketosis if I take diabetes medication?

    That decision belongs to your prescriber before anything changes. Carbohydrate restriction can drop blood sugar quickly in people taking insulin or certain tablets, and some diabetes drugs can cause ketoacidosis even when glucose looks normal. A baseline set of measurements and a plan to repeat them make that conversation specific. The physician’s checklist is in a baseline and re-measure plan before low-carb therapy.

    What does a respiratory quotient tell me about my fuel use?

    It reflects the mix of fat and carbohydrate your body is burning at rest, measured from the gases you breathe after a fast. A lower value points toward fat, a higher value toward carbohydrate. It is a snapshot under set conditions, not a fixed trait, and it shifts with recent meals. Why a measured value beats a formula is explained in measured versus estimated metabolic rate.

    Does insulin resistance in my body mean my brain is insulin resistant?

    Not necessarily, and no blood test can show the brain directly. Body-wide insulin resistance and poorer brain glucose uptake do tend to travel together, and brain tissue from people with Alzheimer’s disease has shown impaired insulin signaling even without diabetes. The body-wide measurement is the one available to you now, which is the argument made in type 3 diabetes and a normal blood sugar.

    Know which fuel your body is using

    Request Measura testing for fasting insulin, a resting respiratory quotient and a cognitive baseline, with the results sent to your physician.

    4477 Woodson Rd, Suite 201, St. Louis, MO 63134. Monday to Friday, 9:00 a.m. to 5:00 p.m. Please do not send symptoms, diagnoses or images through a web form — a website form is not a secure medical channel. Send your name and number and we will call you back.

    References

    • Kula, B., Antal, B., Weistuch, C., Gackière, F., Barre, A., Velado, V., Hubbard, J. M., Kukley, M., Mujica-Parodi, L. R., & Smith, N. A. (2024). D-ꞵ-hydroxybutyrate stabilizes hippocampal CA3-CA1 circuit during acute insulin resistance. PNAS Nexus, 3(5), pgae196. https://doi.org/10.1093/pnasnexus/pgae196
    • Castellano, C. A., Nugent, S., Paquet, N., Tremblay, S., Bocti, C., Lacombe, G., et al., & Cunnane, S. C. (2015). Lower brain 18F-fluorodeoxyglucose uptake but normal 11C-acetoacetate metabolism in mild Alzheimer’s disease dementia. Journal of Alzheimer’s Disease, 43(4), 1343-1353. https://doi.org/10.3233/JAD-141074
    • Croteau, E., Castellano, C. A., Fortier, M., Bocti, C., Fulop, T., Paquet, N., & Cunnane, S. C. (2018). A cross-sectional comparison of brain glucose and ketone metabolism in cognitively healthy older adults, mild cognitive impairment and early Alzheimer’s disease. Experimental Gerontology, 107, 18-26. https://doi.org/10.1016/j.exger.2017.07.004
    • Croteau, E., Castellano, C. A., Richard, M. A., Fortier, M., Nugent, S., Lepage, M., et al., & Cunnane, S. C. (2018). Ketogenic Medium Chain Triglycerides Increase Brain Energy Metabolism in Alzheimer’s Disease. Journal of Alzheimer’s Disease, 64(2), 551-561. https://doi.org/10.3233/JAD-180202
    • Fortier, M., Castellano, C. A., Croteau, E., Langlois, F., Bocti, C., St-Pierre, V., et al., & Cunnane, S. C. (2019). A ketogenic drink improves brain energy and some measures of cognition in mild cognitive impairment. Alzheimer’s & Dementia, 15(5), 625-634. https://doi.org/10.1016/j.jalz.2018.12.017
    • Mujica-Parodi, L. R., Amgalan, A., Sultan, S. F., Antal, B., Sun, X., Skiena, S., et al., & Clarke, K. (2020). Diet modulates brain network stability, a biomarker for brain aging, in young adults. Proceedings of the National Academy of Sciences of the United States of America, 117(11), 6170-6177. https://doi.org/10.1073/pnas.1913042117
    • Graybeal, A. J., Aultman, R. S., Brandner, C. F., Vallecillo-Bustos, A., Compton, A. T., Swafford, S. H., Newsome, T. A., & Stavres, J. (2025). Effects of Ketone Ester Supplementation on Cognition and Appetite in Individuals with and Without Metabolic syndrome: A Randomized Trial. Journal of Dietary Supplements, 22(3), 382-400. https://doi.org/10.1080/19390211.2025.2473371
    • Stubbs, B. J., Stephens, E. B., Mansfield, T., Senadheera, C., Diaz, S. R., Peralta, S., et al. (2025). Exploratory functional and quality of life outcomes with daily consumption of the ketone ester bis-octanoyl (R)-1,3-butanediol in healthy older adults: a randomized, parallel arm, double-blind, placebo-controlled, pilot study. The Journal of Frailty & Aging. https://pubmed.ncbi.nlm.nih.gov/41313689/

    Related reading

  • Older couple working on a crossword puzzle together at a table.

    Brain Insulin Resistance in Alzheimer Disease: Why Type 3 Diabetes

    Brain Insulin Resistance in Alzheimer Disease: Why Type 3 Diabetes

    Brain insulin resistance in Alzheimer disease means the brain both makes less insulin and stops answering it, a pattern found in donated brain tissue even from people without diabetes. That is why the disease was named type 3 diabetes.

    The label came from pathologists holding brain tissue, not from a glucose meter. What they found explains why a normal blood sugar result says little about the brain’s insulin system.

    Alzheimer’s disease earned a diabetes name in a pathology lab, not at a glucose meter. Brain insulin resistance in Alzheimer disease was documented in donated brain tissue, including tissue from people whose charts said they never had diabetes, yet routine care still screens the brain’s fuel problem with a blood sugar test. Measura [Cardiometabolic and Autonomic Health Analysis] cannot look inside a living brain, but it can measure the body-wide insulin picture that travels with it on fasting laboratory panels, years before anyone thinks to ask.

    Where the name type 3 diabetes came from

    In 2005, a team working in Suzanne de la Monte’s laboratory in Providence, Rhode Island, measured the genes that make insulin and its close relatives, the insulin-like growth factors, along with the receptors that receive those signals. Nerve cells normally make some of these hormones themselves. In brains with Alzheimer’s disease, production was sharply reduced, and so were the receptors and the relay proteins that carry the message inward. The researchers described the disease as a hormonal disorder of the brain that resembles diabetes without being identical to it, and they proposed the term type 3 diabetes.

    The combination is the point. Diabetes fails in two ways, too little insulin or cells that stop answering it, and the Alzheimer’s brains were doing both at once.

    What the tissue showed: a message that will not pass

    Low production was only half the story. In 2012, a group led by Konrad Talbot and Steven Arnold studied the hippocampus, the brain’s memory center, from people who had died with Alzheimer’s disease. Its response to insulin signaling was markedly weakened. The breakdown sat at a relay protein called IRS-1, which sits just inside the cell and passes the insulin signal along. In Alzheimer’s tissue, that relay carried chemical tags that switch it off.

    Picture a phone call that connects, rings once and goes dead at the switchboard. Insulin arrives, the receptor picks up, and the relay drops the line.

    Three details lift this work above a curiosity. The people studied did not have diabetes. The off-switch tags rose step by step from normal brains to brains with mild cognitive impairment to brains with Alzheimer’s disease, whether or not the person carried the APOE4 risk gene. And the tags tracked worse memory during life even after the researchers accounted for plaques and tangles, the classic hallmarks of the disease. The same tags also rose with small clumps of amyloid, which suggests the damage runs both ways: amyloid may jam the relay, and a jammed relay may speed decline. Physicians can see the screening side of this in screening for insulin resistance past the glucose.

    Insulin resistance in a brain without diabetes

    This is the part a normal blood sugar result cannot address. Newer autopsy work from the Religious Orders Study, older members of Catholic religious orders in the United States who agreed to yearly testing and brain donation, sharpened the picture. Researchers examined the prefrontal cortex of 150 people, 75 with diabetes matched to 75 without, whose thinking had been tested for a mean of 9.4 years before death.

    The surprising result: brains with more activity at a downstream insulin switch called AKT belonged to people whose memory and overall thinking had declined faster. A signal stuck in the on position is not a healthy signal. It behaves like a car alarm that never stops, which the neighbors soon learn to ignore. A 2025 follow-up in 116 members of the same study found that a growth-factor binding protein tied to Alzheimer’s disease partly carried that relationship, one more sign that the insulin system and the disease process are tangled together.

    The evidence tier, stated once: autopsy tissue shows what was present at death and cannot prove which change came first. It does establish that the brain’s insulin machinery is abnormal in Alzheimer’s disease, and that the abnormality does not wait for a diabetes diagnosis. Research cohorts also favor clean diagnoses. The patient carrying fatty liver, high blood pressure, poor sleep and a thick waist at once, the one with the most insulin in the bloodstream, is the patient these studies were least built to see, so the mechanism has to be applied to that patient rather than waited on. Because the brain can still take up ketones when insulin signaling fails, how ketones reach an insulin-resistant brain is the natural next question.

    The same pattern in living people, years earlier

    Studies in living people use a stand-in called HOMA-IR, a calculation from fasting glucose and fasting insulin that estimates how hard the body is working to keep glucose normal. In Australian adults whose thinking was normal, higher HOMA-IR went with weaker verbal memory, executive function and overall cognition, and with more tau protein in spinal fluid. What that estimate means for your own body is covered in insulin resistance and metabolic health.

    A Finnish study followed the question across two decades. Researchers selected 43 participants by their HOMA-IR at a mean age of 55.1 and tested them again late in life. Over a 5-year stretch ending at a mean age of 74.8, those who had been insulin resistant in midlife lost more episodic memory, the ability to recall events, than those who had been insulin sensitive, and amyloid build-up carried part of that link. For physicians, the broader list of changeable dementia risks is sorted by what a visit can measure in modifiable dementia risk in primary care.

    Why the brain’s insulin problem goes unmeasured

    For years I told patients with borderline blood sugar that their results were not too bad. The tissue work above is part of why I stopped. Two biological forces run under a reassuring glucose: a body pouring out extra insulin to hold glucose in range, and a brain whose insulin relay is being jammed by that flood and by amyloid. A third force is not biological at all. The food supply delivers acellular carbohydrate from breakfast to bedtime, the standard visit is built around glucose and hemoglobin A1c because those numbers define diabetes, and memory is handled in a different office from metabolism. Nobody is assigned to the space between them, where insulin resistance before diabetes quietly builds.

    What a routine visit checks, and what a measurement can show

    No test can see insulin signaling inside a living person’s hippocampus. The tissue studies were done after death, and the brain scans used in research are performed at imaging centers, not by Measura. What can be measured is the body-wide terrain the tissue keeps pointing to, plus a starting point for memory.

    • Blood work. Laboratory panels can include fasting insulin and fasting glucose, the two inputs to HOMA-IR, the estimate the cohort studies used, alongside hemoglobin A1c.
    • A thinking baseline. Cognitive assessment records memory, attention and executive function today, so a later score is compared with your own starting point. More is in memory and cognitive screening.

    Measura measures; it does not diagnose Alzheimer’s disease, and results go to your physician. How a normal glucose can hide the insulin side is covered in type 3 diabetes and a normal blood sugar test.

    The lesson in the name is timing. The tissue shows the insulin relay failing in people without diabetes, and the living cohorts show midlife insulin resistance predicting memory loss decades later. Muscle is the body’s largest glucose sink, and working muscle can pull glucose in through a route that needs less insulin, which is one physiological reason movement and a lighter carbohydrate load reduce the insulin your pancreas must produce. Those levers belong in a conversation with your physician, and they are easier to use when you know where your numbers start. Unmeasured is unmanaged. Questions worth bringing:

    • Has my fasting insulin ever been measured, or only my glucose?
    • Do we have a record of my memory and thinking to compare against later?

    Frequently asked questions

    Is type 3 diabetes an official diagnosis?

    It is a research term, not a diagnosis that appears on a lab report or in your chart. Pathologists proposed it after finding that Alzheimer’s brain tissue made less insulin and responded poorly to it, features of both major kinds of diabetes. Researchers still debate how much it drives the disease. The practical point is that this insulin problem does not appear on a glucose test, as what insulin resistance looks like before diabetes explains.

    Can the brain be insulin resistant if I do not have diabetes?

    The tissue evidence says it can. The hippocampal samples with a blocked insulin relay came from people with Alzheimer’s disease who did not have diabetes, and the relay markers rose through mild cognitive impairment regardless of diabetes status. In living adults with normal thinking, higher insulin resistance tracked weaker memory. A fasting insulin value is one way to see the body-wide side of that problem, described in high insulin with normal blood sugar.

    Does insulin resistance cause Alzheimer’s, or does Alzheimer’s cause insulin resistance?

    The best reading is that both happen. Amyloid clumps can jam the insulin relay in brain cells, and a jammed relay was tied to memory decline even after plaques and tangles were accounted for. Midlife insulin resistance also predicted late-life memory loss in a Finnish cohort. Direction matters less for you than timing, because the insulin side is measurable long before symptoms. The physician’s view is in insulin resistance and dementia screening.

    Why get a cognitive baseline if my memory is fine?

    Because the insulin changes seen in brain tissue start before any memory complaint, and a score has meaning only when there is an earlier one to hold it against. Recording yours while you feel well lets your physician compare you with yourself instead of a population average. The reasoning is laid out in what a cognitive baseline is for.

    How would I know whether my insulin resistance is improving?

    By repeating the same measurements under the same fasting conditions rather than judging by how you feel. Fasting insulin can shift well before glucose does, and glucose may not move at all if it was already in range. Your physician sets the interval and decides what the numbers mean for your care. Practical detail on tracking change is in how to lower insulin resistance and tell whether it worked.

    See your insulin side before symptoms

    Request Measura testing for fasting insulin, a cognitive baseline and the rest of your metabolic picture, with the results sent to your physician.

    4477 Woodson Rd, Suite 201, St. Louis, MO 63134. Monday to Friday, 9:00 a.m. to 5:00 p.m. Please do not send symptoms, diagnoses or images through a web form — a website form is not a secure medical channel. Send your name and number and we will call you back.

    References

    • Steen, E., Terry, B. M., Rivera, E. J., Cannon, J. L., Neely, T. R., Tavares, R., Xu, X. J., Wands, J. R., & de la Monte, S. M. (2005). Impaired insulin and insulin-like growth factor expression and signaling mechanisms in Alzheimer’s disease–is this type 3 diabetes? Journal of Alzheimer’s Disease, 7(1), 63-80. https://doi.org/10.3233/jad-2005-7107
    • Talbot, K., Wang, H. Y., Kazi, H., Han, L. Y., Bakshi, K. P., Stucky, A., et al., & Arnold, S. E. (2012). Demonstrated brain insulin resistance in Alzheimer’s disease patients is associated with IGF-1 resistance, IRS-1 dysregulation, and cognitive decline. The Journal of Clinical Investigation, 122(4), 1316-1338. https://doi.org/10.1172/JCI59903
    • Tong, H., Capuano, A. W., Carmichael, O. T., Gwizdala, K. L., Bennett, D. A., Ahima, R. S., Arnold, S. E., & Arvanitakis, Z. (2024). Brain Insulin Signaling is Associated with Late-Life Cognitive Decline. Aging and Disease, 15(5), 2205-2215. https://doi.org/10.14336/AD.2023.1117
    • Tong, H., Petyuk, V. A., Sendtner, M., Sood, A., Bennett, D. A., Capuano, A. W., & Arvanitakis, Z. (2025). Alzheimer’s disease-related cortical proteins modify the association of brain insulin signaling with cognitive decline. Journal of Alzheimer’s Disease, 104(3), 667-677. https://doi.org/10.1177/13872877251319463
    • Laws, S. M., Gaskin, S., Woodfield, A., Srikanth, V., Bruce, D., Fraser, P. E., et al., & Verdile, G. (2017). Insulin resistance is associated with reductions in specific cognitive domains and increases in CSF tau in cognitively normal adults. Scientific Reports, 7(1), 9766. https://doi.org/10.1038/s41598-017-09577-4
    • Pietilä, E., Karrasch, M., Helin, S., Snellman, A., Viitanen, M., Jula, A., Rinne, J. O., & Ekblad, L. L. (2026). Midlife insulin resistance and brain beta-amyloid accumulation as predictors of change in late-life cognitive function – A 20-year follow-up study. Neurobiology of Aging, 167, 29-41. https://doi.org/10.1016/j.neurobiolaging.2026.06.004

    Related reading

  • Young woman holding a glass soda bottle outdoors.

    Sugar and Gum Inflammation: The Gauge in Your Mouth

    Sugar and Gum Inflammation: The Gauge in Your Mouth

    Sugar drives gum inflammation: young adults eating the most added sugar had about 1.42 times the rate of gum disease, and cutting refined carbohydrate cut gum bleeding by more than half while plaque stayed the same.

    Your gums are the only inflamed tissue you can look at in a mirror. When they bleed, the question worth asking is what else in you is running hot.

    Almost every tissue that sugar inflames is hidden. Sugar and gum inflammation is the exception: the gums are the one inflamed surface in your body you can look at in a mirror, and they bleed on contact when something is wrong. That makes them a gauge, and it makes the standard advice about them oddly small. Brush better, floss more, come back in six months. The gauge is reporting on your metabolism, and almost nobody reads it that way, even though the blood markers of insulin resistance and inflammation are a routine draw.

    What the mouth evidence actually shows

    Start with intake rather than brushing. Among 2437 adults aged 18 to 25 in the third National Health and Nutrition Examination Survey, those in the highest third of added sugar consumption had about 1.42 times the prevalence of periodontal disease compared with the lowest, after adjustment for smoking, poverty, education, body mass index and known diabetes. The association was stronger the more teeth were involved, at about 1.73 times for disease in two or more teeth. In a later analysis of the same survey covering 4473 adults aged 30 to 50, the heaviest sugar-sweetened beverage drinkers carried roughly 2.19 times the odds of periodontitis.

    Those are observational, and diet questionnaires are blunt instruments. The experiments that follow are small and short, and none was built around the patient with diabetes, obesity and a long medication list, because trials isolate one variable and that patient is the one they leave out. They push the same way under control. In a randomized pilot, adults who switched for 4 weeks to a diet low in refined carbohydrate and richer in omega-3 fats, vitamins C and D, antioxidants and fiber cut bleeding on probing from 53.57% of sites to 24.17%, while their plaque scores did not change. A second randomized trial of an anti-inflammatory diet reproduced the drop in gum bleeding, again with plaque unchanged.

    The strangest result is the most instructive. Ten volunteers lived for 4 weeks in a reconstructed Stone Age settlement with no toothbrushes, no floss and no refined sugar. Plaque rose, as it must, from 0.68 to 1.47 on the index used. Bleeding fell anyway, from 34.8% of sites to 12.6%. Plaque was not what drove the inflammation; what the plaque was being fed was.

    Two engines, one visible symptom

    The first engine is local and microbial. Fermentable sugar arriving several times a day shifts which organisms thrive in the film on your teeth and below the gumline, and the shifted community is the one that provokes an immune response. Brushing is necessary and not sufficient: you are removing a film whose composition is set by what you eat.

    The second engine is systemic, and it has a name: metaflammation. Excess fructose and sucrose produce low-grade inflammation throughout the body and shift both the oral and the intestinal microbial community, so the gums are inflamed by something that is also inflaming tissue you cannot see. Your gut is the first brain in this sequence, taking delivery of the load; the mouth is the window onto it. The third driver is neither microbial nor metabolic. Added sugar is built into most packaged and restaurant food, so the exposure repeats whether or not anyone chose it. That is an engineering decision made upstream of your kitchen, which is why measuring the host rather than the additive is the practical response. Inside the arteries, a thin sugar coating takes the same hit after every spike, described in the lining that high blood sugar strips first.

    The number the dental chart cannot give you

    In 3616 adults without diabetes in the continuous National Health and Nutrition Examination Survey for 1999 to 2004, insulin resistance rose with the depth of the pockets around the teeth: each additional millimeter of average probing depth went with a 1.04-fold higher insulin resistance score. The association concentrated in people whose white cell count was already high, where the deepest quartile of probing depth carried about 2.60 times the risk of marked insulin resistance. Inflammation was both the middle step and the condition that decided who was affected. Glucose can sit in range through all of it, which is why fasting insulin beside a normal A1C says more.

    A small pilot took the question to people in their early twenties. Of 20 patients with no diabetes diagnosis, the high-sugar group had a mean insulin resistance score of 2.52 against 1.60 in the low-sugar group, and their measured area of inflamed gum ran 329.44 square millimeters against 54.02. That is cross-sectional and tiny, a direction rather than a finding.

    The longitudinal evidence is what changed recently. A 2026 systematic review of 28 longitudinal studies covering more than 300,000 participants found that people with periodontitis at the start were 18 to 25% more likely to be newly diagnosed with type 2 diabetes during follow-up, with the relationship running both ways. In a Korean national cohort of 43,713 adults followed for up to nine years, severe periodontitis carried about a 1.10-fold higher risk of developing metabolic syndrome, strongest in people in their fifties. Bleeding gums prove nothing metabolic in any one person. Across populations, they run ahead of trouble. Joints that carry no weight tell a similar metabolic story, covered for clinicians in metabolic screening in hand osteoarthritis.

    What a routine visit checks, and what it leaves out

    Your dentist measures pocket depth, bleeding and bone loss. Your physician records weight and blood pressure and may order a glucose or an A1C. Both are doing their jobs, and the two charts rarely meet. Nothing in that sequence asks the question the evidence raises: is the inflammation in this person’s mouth keeping company with insulin resistance, an inflammatory signal in the blood, and fat in the wrong compartment? Who should be tested lists the patterns that justify asking.

    Measuring the body the gums belong to

    Say the limit first. Measura [Cardiometabolic and Autonomic Health Analysis] does not examine gums, does not probe pockets and has no saliva or microbial test. A dentist or periodontist does that work, and nothing here replaces it. Measura is a testing service that measures the body those gums belong to and sends findings to your physician.

    • Laboratory panels cover fasting insulin reported beside glucose and A1C, and inflammatory markers including high-sensitivity C-reactive protein. Insulin rises years before glucose moves, which is the window the studies above describe.
    • Bioimpedance body composition separates fat from muscle, so a normal weight stops standing in for a normal metabolism.

    One timing detail: an inflammatory marker drawn the day after a deep cleaning reads high because of the cleaning, so space them. For the sugar side in more depth, does sugar cause inflammation follows fructose through the liver and the fat cell, and gum disease and dementia handles the brain claim and what the evidence supports. Why the pull toward sugar is not a willpower story is covered in what causes sugar cravings.

    What to ask for, at two appointments

    At the dentist, ask for a full-mouth examination rather than a spot check, and ask for your bleeding percentage, so you have a number to compare later. At your physician, ask for fasting insulin alongside glucose and an inflammatory marker, and say out loud that your gums bleed, because that sentence rarely reaches a medical chart.

    Then change the input, not just the brushing. The diet experiments above halved gum bleeding in four weeks with no change in hygiene, which makes your own gums a fast, visible check on whether a dietary change reached your tissues. Results go to your physician, who decides what they mean, and medication changes belong in that conversation. Insulin resistance and metabolic health explains what the blood work looks for. Unmeasured is unmanaged, and this is the rare case where the first gauge is one you can read yourself.

    Frequently asked questions

    Do bleeding gums mean I have a blood sugar problem?

    Not on their own. Bleeding means inflamed gum tissue, which has plenty of local causes, and many people with gingivitis have unremarkable metabolic numbers. What the population data show is that periodontitis runs ahead of new type 2 diabetes and metabolic syndrome often enough to be worth checking rather than assuming. The way to settle it in your case is measurement. What insulin resistance looks like before diabetes explains the early stage.

    If plaque is not the main problem, should I stop flossing?

    Keep flossing. In the Stone Age study, bleeding fell despite rising plaque because refined sugar was gone, not because plaque is harmless, and that setting is nothing like a modern diet. The honest reading is that mechanical cleaning and dietary sugar are two separate levers on the same tissue, and most people are pulling only one of them. Metaflammation screening covers the systemic lever.

    Can Measura test my gums or my mouth bacteria?

    Neither one. There is no dental examination, no saliva test and no microbial panel here, and a periodontal diagnosis belongs to a dentist or periodontist. What Measura measures is the metabolic picture in the same person: fasting insulin and glucose, inflammatory markers, and the split between fat and muscle, with findings sent to your physician. What Measura actually measures lists the full set.

    How fast would cutting sugar change anything measurable?

    Gum bleeding moved within four weeks in both diet experiments, which is quick because inflamed gum tissue turns over fast. Blood markers of insulin resistance and body composition move on a slower schedule, usually months, and they need the same test repeated under the same conditions to be interpretable. That is why a baseline taken before you change anything is worth having. How to lower insulin resistance covers tracking it.

    Measure the body behind the bleeding

    Request Measura testing for fasting insulin, inflammatory markers and body composition, with results sent to your physician to read alongside your dental care.

    4477 Woodson Rd, Suite 201, St. Louis, MO 63134. Monday to Friday, 9:00 a.m. to 5:00 p.m. Please do not send symptoms, diagnoses or images through a web form — a website form is not a secure medical channel. Send your name and number and we will call you back.

    References

    • Shanmugasundaram, S., & Karmakar, S. (2024). Excess dietary sugar and its impact on periodontal inflammation: a narrative review. BDJ Open, 10(1), 78. https://doi.org/10.1038/s41405-024-00265-w
    • Lula, E. C., Ribeiro, C. C., Hugo, F. N., Alves, C. M., & Silva, A. A. (2014). Added sugars and periodontal disease in young adults: an analysis of NHANES III data. The American Journal of Clinical Nutrition, 100(4), 1182-1187. https://doi.org/10.3945/ajcn.114.089656
    • Alves-Costa, S., Nascimento, G. G., Peres, M. A., Li, H., Costa, S. A., Ribeiro, C. C. C., & Leite, F. R. M. (2024). Sugar-sweetened beverage consumption and periodontitis among adults: A population-based cross-sectional study. Journal of Clinical Periodontology, 51(6), 712-721. https://doi.org/10.1111/jcpe.13961
    • Demmer, R. T., Squillaro, A., Papapanou, P. N., Rosenbaum, M., Friedewald, W. T., Jacobs, D. R., & Desvarieux, M. (2012). Periodontal infection, systemic inflammation, and insulin resistance: results from the continuous National Health and Nutrition Examination Survey (NHANES) 1999-2004. Diabetes Care, 35(11), 2235-2242. https://doi.org/10.2337/dc12-0072
    • Woelber, J. P., Bremer, K., Vach, K., Konig, D., Hellwig, E., Ratka-Kruger, P., Al-Ahmad, A., & Tennert, C. (2016). An oral health optimized diet can reduce gingival and periodontal inflammation in humans – a randomized controlled pilot study. BMC Oral Health, 17(1), 28. https://doi.org/10.1186/s12903-016-0257-1
    • Woelber, J. P., Gartner, M., Breuninger, L., Anderson, A., Konig, D., Hellwig, E., Al-Ahmad, A., Vach, K., Dotsch, A., Ratka-Kruger, P., & Tennert, C. (2019). The influence of an anti-inflammatory diet on gingivitis. A randomized controlled trial. Journal of Clinical Periodontology, 46(4), 481-490. https://doi.org/10.1111/jcpe.13094
    • Baumgartner, S., Imfeld, T., Schicht, O., Rath, C., Persson, R. E., & Persson, G. R. (2009). The impact of the stone age diet on gingival conditions in the absence of oral hygiene. Journal of Periodontology, 80(5), 759-768. https://doi.org/10.1902/jop.2009.080376
    • Caleb, C. L., Dharuman, S., Sundhar, M. P., Chellapandi, S., & Balaji, U. G. (2025). Evaluation of the association between insulin resistance and the development of periodontitis in individuals with varying levels of dietary sugar intake – A pilot study. Journal of Indian Society of Periodontology, 29(3), 279-283. https://doi.org/10.4103/jisp.jisp_125_24
    • Botelho, J., Singh, S., Varenne, B., Rendell, N., Harada, Y., Proenca, L., Machado, V., & Valentim Bitencourt, F. (2026). Oral health and diabetes: a systematic review and meta-analysis. The Lancet Public Health, 11(8), e555-e566. https://doi.org/10.1016/S2468-2667(26)00149-0
    • Hwang, S., Kim, H. Y., Kang, S., Kim, J., Song, S., & Park, G. R. (2026). Association of periodontitis with incidence of metabolic syndrome in Korea: A retrospective cohort study. Journal of Periodontology. https://doi.org/10.1002/jper.70169

    Related reading

  • Woman in activewear measuring her waist with a tape measure in a gym.

    Can Belly Fat Cause Chronic Pain? What 32,409 MRI Scans Show

    Can Belly Fat Cause Chronic Pain? What 32,409 MRI Scans Show

    Belly fat is tied to chronic pain: in abdominal MRI scans of 32,409 adults, more visceral and subcutaneous fat meant pain in more parts of the body, most strongly in women.

    Aching in your back, knees and shoulders at once gets filed under getting older. Large MRI studies point to a different common thread: where your body stores fat.

    Can belly fat cause chronic pain? When your back, knees and shoulders all hurt at once, you leave with three explanations, three referrals and the word arthritis. Abdominal MRI scans of 32,409 adults point to one common thread instead: the fat stored deep inside your abdomen rises in step with the number of places that hurt, most of all in women, and a scale cannot see it, though a body composition test gets you closer.

    What the MRI study measured

    Researchers at the University of Tasmania used the UK Biobank, a long-running British health study, to examine adults who had abdominal MRI scans (50.8% women, average age 55.0). The scans split belly fat into two compartments. Visceral fat sits inside the abdominal wall, packed around the intestines and liver. Subcutaneous fat sits under the skin, the part you can pinch. Participants reported pain in the neck or shoulder, back, hip or knee, or pain all over the body, and many were scanned and questioned again at a second imaging visit.

    As each type of fat went up, the count of painful sites went up with it, step by step, in both sexes. Higher levels of adipose tissue were also associated with greater odds of reporting chronic pain in both sexes, not just pain in more places.

    Visceral fat, subcutaneous fat and pain in women and men

    • Women. Each standard-deviation rise in visceral fat came with 2.04 times the odds of pain in more sites. For subcutaneous fat the figure was 1.60.
    • Men. The odds rose 1.34 times for visceral fat and 1.39 times for subcutaneous fat.

    The ratio of visceral to subcutaneous fat tracked pain as well, and the authors attribute the larger effect in women to sex differences in fat storage and hormones. Why the two compartments behave differently is covered in the difference between visceral and subcutaneous fat.

    In men, the pinchable fat under the skin carried as much pain risk as the deep fat around the organs. The comfortable story that outer fat is the harmless kind collapses the moment you ask about pain.

    This is an observational study, and the arrow runs both ways: pain cuts movement, stillness stores fat, fat feeds pain. What the data demolish is the idea that aching in four places is four separate cases of wear and tear.

    Why fat in the belly makes the whole body hurt

    A knee carries body weight. A neck does not carry more of it when your waist grows, yet the neck hurt more too. Load cannot explain that. Something traveling in the blood can, and the authors conclude that fat stored where it does not belong is involved in how multisite pain develops.

    Two biological drivers run the cascade. The first is fat behaving as an organ. Swollen fat tissue around the abdomen releases inflammatory messengers into the circulation, a steady low-grade fire called metaflammation, and inflamed nerve endings fire at lower thresholds, so ordinary pressure and ordinary movement start to register as pain. The second is insulin. Deep abdominal fat and a fat-loaded liver force the pancreas to pour out more insulin to keep blood sugar normal, and that strained metabolism starves small nerves and slows the repair of muscles and tendons after every day of use.

    The third driver is economic, and it is the one nobody writes on a prescription pad. Agricultural subsidies make acellular carbohydrates and industrial seed oils the most available calories in the country, most jobs keep people seated all day, and a person who already hurts moves less and sleeps worse. Every one of those loads the abdominal depot. None of it is a willpower failure. It is a food system and a work system doing exactly what they were built to do. Chronic stress feeds the same depot through its own hormonal loop, traced in how cortisol and belly fat feed each other. The timing of the stress response matters as much as its size, which is where gut bacteria and the daily stress rhythm come in.

    What your weight and BMI cannot tell you

    A second UK Biobank analysis looked at 500,107 adults aged 40 to 69 and compared ways of describing body fat. Body fat percentage measured by bioimpedance, a small electrical signal passed through the body, correlated with body mass index at 0.85 in women and 0.80 in men. Total fat and body mass index mostly tell the same story. Shape told a different one: waist-to-hip ratio was the only measure still tied to a higher risk of death after full adjustment, 1.21 in women and 1.19 in men when the highest and lowest ends of the range were compared.

    A third analysis of abdominal MRI from 33,889 UK Biobank participants linked visceral fat, fat infiltrating the muscles along the spine, and chronic back pain in both sexes. Your scale answers how much. Your pain is answering where. The practical ways to measure the second question are laid out in how to measure visceral fat when the scale says you are fine. Clinicians have a waist-to-weight ratio that flags this depot in older patients with high blood pressure, described in the weight-adjusted waist index and stroke.

    What happens to pain when the weight comes off

    For years I treated the joint that hurt and handed the waistline a pamphlet. The trial evidence has made that division indefensible. In STEP 9, 407 adults with obesity and painful knee osteoarthritis (81.6% women, average body mass index 40.3) were followed for 68 weeks. Everyone received counseling on physical activity and a reduced-calorie diet; two thirds also received a weekly weight-loss injection and the rest a placebo. Weight fell 13.7% with the drug and 3.2% with placebo. On a pain scale of 0 to 100, pain dropped 41.7 points with the drug and 27.5 points with placebo.

    Look hard at the placebo group: a modest loss on counseling alone, and their pain still fell. The people who lost the most weight hurt the least. Nothing here is a reason to start or stop any medication; that decision belongs to you and your physician.

    No trial has yet tested whether shrinking visceral fat eases pain in several body sites, because trials enroll one diagnosis at a time and screen out the person with metabolic disease, obesity and pain in four places, the exact person the MRI study describes. The mechanism has to carry the decision. Movement, sleep and food are treatment, each with a physiological why: contracting muscle pulls sugar out of the blood without extra insulin, deep sleep lowers the inflammatory tone that sensitizes nerves, and cutting acellular carbohydrates lowers the insulin load that locks fat in the abdominal depot. The fat that drives pain is also tied to cancer risk, laid out in how weight and metabolic dysfunction connect to cancer.

    Is pain from belly fat also a warning about the heart?

    The people the MRI study describes, carrying visceral fat and hurting in several places, also carry a heart risk that rarely comes up at a pain visit. Among 475,171 UK Biobank participants followed for a median of seven years, chronic widespread pain was tied to a 48% higher risk of heart attack, stroke, heart failure or cardiovascular death after adjusting for standard risk factors, inflammatory disease and pain medication. The share of cardiovascular disease attributable to chronic pain, 8.6%, was comparable with the share attributable to diabetes, 7.3%. A 2026 meta-analysis of 18 studies found the link between widespread pain and atherosclerotic disease held after full adjustment, while the link to cardiovascular death was weaker and not statistically clear.

    That is one terrain with two symptoms. The inflammation that sensitizes nerves also shows up in the blood, and what a high-sensitivity CRP number says about your heart explains how to read it. How the load of fat and the sickness of fat each reach the heart is laid out in obesity and heart disease.

    What measurement can show

    Measura [Cardiometabolic and Autonomic Health Analysis] is a testing service. It measures, it does not treat, and results go to your physician. It does not perform MRI; imaging that separates visceral from subcutaneous fat is done elsewhere. What Measura adds in the same person:

    • Bioimpedance body composition estimates fat mass and muscle mass separately. It cannot isolate visceral fat, but repeat tests show whether you are losing muscle while keeping fat.
    • Laboratory panels can include fasting insulin and high-sensitivity C-reactive protein, the metabolic and inflammatory output of that fat, which a glucose-only panel never sees.

    How pain and metabolism connect in everyday care is covered in chronic pain and metabolic health. Unmeasured is unmanaged, and a pain nobody traces to its terrain gets managed forever.

    What to ask at your next visit

    • Has anyone measured where my fat sits, or only what I weigh?
    • Can my blood work include fasting insulin and an inflammation marker, not just glucose?
    • If I lose weight, how will we know whether it came from fat or from muscle?

    More questions worth bringing are in questions to ask a pain management doctor about your numbers, and holding on to a loss once it happens is covered in how to maintain weight loss when the scale stops telling the truth.

    Frequently asked questions

    Is visceral fat worse than the fat I can pinch?

    For heart and metabolic risk, deep visceral fat carries more weight. For pain, the MRI study found both matter: in women visceral fat had the stronger link, while in men the fat under the skin was linked to pain as strongly as the fat around the organs. Neither kind can be judged from a scale reading. Visceral fat vs subcutaneous fat: what testing can show explains the difference in more detail.

    Why would belly fat make my neck or shoulders hurt?

    Abdominal fat does not press on your neck, which is why the explanation lives in the blood. Inflammatory messengers released from swollen fat tissue make nerves more sensitive throughout the body, so pain shows up far from the fat itself. When the nervous system turns up its volume like this, the pattern has its own name, covered in central sensitization symptoms and what your numbers can show.

    Can chronic stress add belly fat and pain at the same time?

    Stress hormones push fat storage toward the middle, and poor sleep and constant pain raise the stress load further, so the two problems feed each other. The waist and the blood fats record that loop faithfully. The mechanism is explained in cortisol and belly fat: what chronic stress leaves you can measure.

    Does a normal blood sugar mean my metabolism is fine?

    Not necessarily. Blood sugar can stay in range for years while the pancreas makes more and more insulin to hold it there, and that high insulin is part of what keeps abdominal fat stored. A fasting insulin level alongside glucose and hemoglobin A1c shows the problem years earlier. Why that matters when you hurt is covered in what a normal A1c can hide when you hurt.

    Can a scale show whether I lost the right kind of weight?

    A scale reports one total. It cannot tell you whether the pounds that left were fat or muscle, and losing muscle while keeping abdominal fat can leave pain and metabolism untouched even as the number drops. Body composition testing splits that total into its parts and can be repeated to show a trend. The reasoning is laid out in body composition is not the same as weight.

    Find out where your body stores fat

    Ask about body composition and metabolic blood work so your physician can see what a scale reading leaves out. Request testing through Measura.

    4477 Woodson Rd, Suite 201, St. Louis, MO 63134. Monday to Friday, 9:00 a.m. to 5:00 p.m. Please do not send symptoms, diagnoses or images through a web form — a website form is not a secure medical channel. Send your name and number and we will call you back.

    References

    • Kifle, Z. D., Tian, J., Aitken, D., Melton, P. E., Cicuttini, F., Jones, G., & Pan, F. (2026). MRI-derived abdominal adipose tissue is associated with multisite and widespread chronic pain. Regional Anesthesia and Pain Medicine, 51(4), 371-378. https://doi.org/10.1136/rapm-2024-105535
    • Wiebe, N., & Tonelli, M. (2025). Associations of body fat and inflammation with non-communicable chronic diseases and mortality: a prospective cohort study of the UK Biobank. BMJ Open, 15(10), e092962. https://doi.org/10.1136/bmjopen-2024-092962
    • Niglas, M., Whitcher, B., Amiras, D., Thanaj, M., Basty, N., Bell-Bradford, C., Thomas, E. L., & Bell, J. D. (2026). Detecting scoliosis at scale using automated cobb angle analysis in the UK biobank. European Spine Journal. https://doi.org/10.1007/s00586-026-10239-1
    • Bliddal, H., Bays, H., Czernichow, S., Uddén Hemmingsson, J., Hjelmesæth, J., Hoffmann Morville, T., Koroleva, A., Skov Neergaard, J., et al. (2024). Once-weekly semaglutide in persons with obesity and knee osteoarthritis. The New England Journal of Medicine, 391(17), 1573-1583. https://doi.org/10.1056/NEJMoa2403664
    • Rönnegård, A.-S., Nowak, C., Äng, B., & Ärnlöv, J. (2022). The association between short-term, chronic localized and chronic widespread pain and risk for cardiovascular disease in the UK Biobank. European Journal of Preventive Cardiology, 29(15), 1994-2002. https://doi.org/10.1093/eurjpc/zwac127 (PMID 35727954)
    • Rönnegård, A.-S., Schillemans, T., Äng, B., Boersma, K., Ärnlöv, J., & Tseli, E. (2026). Chronic widespread pain and the risk of cardiovascular disease-a systematic review and meta-analysis. Pain, 167(6), 1295-1307. https://doi.org/10.1097/j.pain.0000000000003965 (PMID 41972388)

    Related reading

  • Dr. Gurpreet Singh Padda beside the title card reading There Is No Discharge Date, The Angry Gut, Chapter 30

    How to Maintain Weight Loss When the Scale Stops Telling the Truth

    There Is No Discharge Date | The Angry Gut, Chapter 30

    How to Maintain Weight Loss When the Scale Stops Telling the Truth

    To maintain weight loss, measure more than weight: repeat body composition to see whether fat or muscle came back, a laboratory panel for insulin and glycemic drift, and resting energy use measured by indirect calorimetry. There is no fixed end point; the workload falls with time, but the checking does not.

    Losing the weight is the part everyone plans for. The year after, when support thins out and only the scale is watching, is where most results quietly leak away.

    Most people who lose weight get one instruction for afterward: keep weighing yourself. That makes the scale the maintenance instrument, and the scale is the one number that cannot tell you whether you kept the right thing. If you are searching how to maintain weight loss, the better question is what is actually holding underneath the pounds a year later.

    The video There Is No Discharge Date, from The Angry Gut by Dr. Gurpreet Singh Padda, MD, MBA, MHP, and Ami Michelle Grimes, answers a patient who is finally well and wants to know when he can stop. He cannot stop, but the work gets lighter each year. Measurement is how you confirm it is getting lighter without sliding backward.

    Why maintenance fails quietly

    Two biological drivers pull a body back toward where it started. The first lives in the gut, the first brain. Its microbial community answers to food on a clock measured in days: volunteers moved onto an animal-based diet with almost no fiber saw their community shift within a day and swing back two days after the diet ended. The deeper arrangement of that community, its enterotype, follows years of eating instead. A vacation moves the quick layer. A decade of habit moves the slow one. The second brain, in your skull, receives reports from both.

    The second driver is insulin resistance and the low-grade inflammation that rides along with it, metaflammation. Neither shows up on a scale. In mice, a microbiome altered by earlier obesity persisted after successful dieting, sped up regain, and passed that tendency on to mice raised without their own microbes, with the regain traced to lower flavonoid levels and reduced energy expenditure. That is animal work with no human confirmation yet, and it is still the clearest mechanism on record for why a body does not simply stay where the diet left it.

    The third driver is economic. Pooled studies set a helpful daily fiber target of 25 to 29 grams, far above what most Americans eat, because the cheap default in the grocery store is refined starch with the husk removed. Maintenance programs are then built as if people will keep showing up on their own.

    What the long trials say about keeping it off

    The landmark prevention trial gave adults with impaired glucose tolerance a 7% weight-loss target and 150 minutes of weekly activity. New diabetes fell by 58%, against 31% on metformin. Fifteen years later the gap had narrowed: cumulative diabetes reached 55% with lifestyle, 56% on metformin and 62% on placebo. Participants who never developed diabetes, whatever arm they were in, showed 28% fewer complications in the small blood vessels, so the result a person reached mattered more than the group they started in.

    In adults who already had type 2 diabetes, intensive support produced 8.6% weight loss at one year, which wore down to 6.0% against 3.5% in the comparison group, and the trial was stopped for futility at 9.6 years. In the national prevention program, 35.5% of enrollees hit the 5% goal, median attendance was 14 sessions, and every extra session attended went with another 0.3% of body weight lost.

    Put those side by side and one pattern stands out. Intensity fades, and results fade with it. That is not a judgment about willpower. It is a dosing problem, and a dosing problem can be tracked.

    What a routine follow-up checks, and what it misses

    A typical maintenance visit records weight, blood pressure and perhaps a glucose marker. Each has value. None of them answers the questions that decide whether the loss is holding in the way that protects you:

    • What came back, fat or muscle? The two read the same on a bathroom scale and mean very different things for your metabolism.
    • Is the metabolic load drifting? Blood sugar can sit in range while the underlying insulin resistance creeps back.
    • Has resting energy use changed? A formula assumes an average body. Yours just changed shape.

    Tissue shows what a delivered dose can do. In a 52-week study of people with steatohepatitis confirmed on biopsy, 25% saw the liver inflammation resolve overall, yet among those who lost 10% or more of their weight, 90% had resolution and 45% had scarring regress. Liver biopsy and liver imaging are separate tests done elsewhere, not Measura tests. The lesson is that the amount of change delivered, not the name of the plan, moved the tissue.

    How to maintain weight loss over time

    Measura [Cardiometabolic and Autonomic Health Analysis] is a testing service. It measures and sends the findings to your physician; it does not diagnose disease or treat it. For someone in the maintenance phase, four measurements line up with the drivers above:

    No single result is the point. The same measurements, repeated, make change visible while it is still small. Timing is covered in how often to repeat cardiometabolic testing.

    Adherence is the dose, and it can be seen

    For years I ended visits by jotting a line about eating better and moving more, and I counted it as a plan. It was a wish with no instrument attached. What changed my mind was watching numbers follow what people actually did rather than what they were told. In a year-long Mediterranean diet trial in older adults, microbial change scaled with how closely people followed the diet, not with their assigned group, and the favored organisms tracked with less frailty and lower inflammatory markers.

    Food tools also do different jobs in the first brain. In a seventeen-week trial in healthy adults, fiber expanded the community’s machinery for breaking down complex carbohydrates without raising diversity, while fermented food raised diversity and lowered 19 of 93 circulating inflammatory proteins. No Measura test reads your microbiome; stool and breath tests are done elsewhere. What a repeat visit can follow is the metabolic picture downstream of it.

    Capability counts as well. Among insured patients in primary care, activation, the know-how and confidence to run your own care, lined up with 12 of 13 outcomes in the expected direction. A report you can read for yourself feeds that directly, and understanding your results walks through one.

    What to ask at your next visit

    • Can my follow-up include body composition, not just weight?
    • Can insulin be checked alongside my glucose markers, and repeated on a schedule?
    • What is the smallest version of this plan I could still be doing a year from now?
    • If adding fiber makes me feel worse, is the order of the plan the problem rather than the fiber?

    No discharge date does not mean effort forever at the same level. It means the effort shrinks while the checking continues. The barrier work this maintenance protects is in the gut-wall post, and the people who stay unwell anyway are the subject of how to test for mast cell activation. The Chapter 30 Deep Dive carries each study cited here along with what it cannot show.

    Frequently asked questions

    How long do you have to keep up lifestyle changes after losing weight?

    There is no fixed end point. Fifteen years into the best-known prevention study, people assigned to lifestyle change still kept an edge, though a smaller one, and in adults with type 2 diabetes, weight loss eroded as support tapered. The workload can fall with time. The need to keep checking your numbers does not. Read about insulin resistance and metabolic health.

    Why does weight come back even when I eat the same way?

    Behavior is only part of it. In mice, a gut community changed by past obesity persisted after dieting, sped up regain, and was linked to reduced energy expenditure. That has not been confirmed in people. Your own resting energy use can be measured directly rather than guessed from a formula, which helps set realistic targets. See how metabolic rate and energy are measured.

    Is weight the best number to track during maintenance?

    It is the easiest, not the best. Weight cannot separate fat regained from muscle lost, and the two carry very different metabolic consequences. Pairing weight with body composition and a repeat laboratory panel shows whether the loss that protects you is holding. Learn why body composition is not the same as weight.

    Can Measura test my gut microbiome?

    No. Stool, breath and microbiome tests are different tests done elsewhere, and a stool species list mainly reports what left the body. Measura measures the metabolic, autonomic, vascular and body composition picture in the same person, which is where changes in the gut often show up downstream. See what Measura actually measures.

    What should I bring to a maintenance visit?

    Bring your earlier results so change can be compared, a list of every medication and supplement, and an honest account of what you are still doing day to day. Ask which measurements will be repeated and when, so the visit tracks a trend instead of a single snapshot. Get a list of questions worth asking your doctor.

    Check what your weight loss is really holding

    Ask about repeat body composition, laboratory and metabolic rate testing so your physician can see a trend, not just a number on a scale.

    4477 Woodson Rd, Suite 201, St. Louis, MO 63134. Monday to Friday, 9:00 a.m. to 5:00 p.m. Please do not send symptoms, diagnoses or images through a web form — a website form is not a secure medical channel. Send your name and number and we will call you back.

    References

    • Knowler, W. C., Barrett-Connor, E., Fowler, S. E., Hamman, R. F., Lachin, J. M., Walker, E. A., Nathan, D. M., & Diabetes Prevention Program Research Group. (2002). Reduction in the incidence of type 2 diabetes with lifestyle intervention or metformin. N Engl J Med, 346(6), 393-403. https://doi.org/10.1056/NEJMoa012512
    • Diabetes Prevention Program Research Group. (2015). Long-term effects of lifestyle intervention or metformin on diabetes development and microvascular complications over 15-year follow-up: the Diabetes Prevention Program Outcomes Study. Lancet Diabetes Endocrinol, 3(11), 866-75. https://doi.org/10.1016/S2213-8587(15)00291-0
    • Wing, R. R., Bolin, P., Brancati, F. L., Bray, G. A., Clark, J. M., Coday, M., Crow, R. S., Curtis, J. M., Egan, C. M., Espeland, M. A., Evans, M., Foreyt, J. P., Ghazarian, S., Gregg, E. W., Harrison, B., Hazuda, H. P., Hill, J. O., Horton, E. S., Hubbard, V. S., … Yanovski, S. Z. (2013). Cardiovascular effects of intensive lifestyle intervention in type 2 diabetes. N Engl J Med, 369(2), 145-54. https://doi.org/10.1056/NEJMoa1212914
    • Ely, E. K., Gruss, S. M., Luman, E. T., Gregg, E. W., Ali, M. K., Nhim, K., Rolka, D. B., & Albright, A. L. (2017). A National Effort to Prevent Type 2 Diabetes: Participant-Level Evaluation of CDC’s National Diabetes Prevention Program. Diabetes Care, 40(10), 1331-1341. https://doi.org/10.2337/dc16-2099
    • Thaiss, C. A., Itav, S., Rothschild, D., Meijer, M. T., Levy, M., Moresi, C., Dohnalova, L., Braverman, S., Rozin, S., Malitsky, S., Dori-Bachash, M., Kuperman, Y., Biton, I., Gertler, A., Harmelin, A., Shapiro, H., Halpern, Z., Aharoni, A., Segal, E., & Elinav, E. (2016). Persistent microbiome alterations modulate the rate of post-dieting weight regain. Nature, 540(7634), 544-551. https://doi.org/10.1038/nature20796
    • Vilar-Gomez, E., Martinez-Perez, Y., Calzadilla-Bertot, L., Torres-Gonzalez, A., Gra-Oramas, B., Gonzalez-Fabian, L., Friedman, S. L., Diago, M., & Romero-Gomez, M. (2015). Weight Loss Through Lifestyle Modification Significantly Reduces Features of Nonalcoholic Steatohepatitis. Gastroenterology, 149(2), 367-78.e5. https://doi.org/10.1053/j.gastro.2015.04.005
    • Ghosh, T. S., Rampelli, S., Jeffery, I. B., Santoro, A., Neto, M., Capri, M., Giampieri, E., Jennings, A., Candela, M., Turroni, S., Zoetendal, E. G., Hermes, G. D. A., Elodie, C., Meunier, N., Brugere, C. M., Pujos-Guillot, E., Berendsen, A. M., De Groot, L. C. P. G. M., Feskins, E. J. M., … O’Toole, P. W. (2020). Mediterranean diet intervention alters the gut microbiome in older people reducing frailty and improving health status: the NU-AGE 1-year dietary intervention across five European countries. Gut, 69(7), 1218-1228. https://doi.org/10.1136/gutjnl-2019-319654
    • Wastyk, H. C., Fragiadakis, G. K., Perelman, D., Dahan, D., Merrill, B. D., Yu, F. B., Topf, M., Gonzalez, C. G., Van Treuren, W., Han, S., Robinson, J. L., Elias, J. E., Sonnenburg, E. D., Gardner, C. D., & Sonnenburg, J. L. (2021). Gut-microbiota-targeted diets modulate human immune status. Cell, 184(16), 4137-4153.e14. https://doi.org/10.1016/j.cell.2021.06.019
    • David, L. A., Maurice, C. F., Carmody, R. N., Gootenberg, D. B., Button, J. E., Wolfe, B. E., Ling, A. V., Devlin, A. S., Varma, Y., Fischbach, M. A., Biddinger, S. B., Dutton, R. J., & Turnbaugh, P. J. (2014). Diet rapidly and reproducibly alters the human gut microbiome. Nature, 505(7484), 559-63. https://doi.org/10.1038/nature12820
    • Greene, J., & Hibbard, J. H. (2012). Why does patient activation matter? An examination of the relationships between patient activation and health-related outcomes. J Gen Intern Med, 27(5), 520-6. https://doi.org/10.1007/s11606-011-1931-2

    Related reading

  • Dr. Gurpreet Singh Padda beside the title card The Weeds Were Never the Problem, The Angry Gut, Chapter 27

    Probiotics After Antibiotics: What Recovery Actually Looks Like

    The Weeds Were Never the Problem | The Angry Gut, Chapter 27

    Probiotics After Antibiotics: What Recovery Actually Looks Like

    In the strongest study of probiotics after antibiotics, a multi-strain capsule delayed the return of the gut’s native community compared with recovering unaided, while a transplant of the person’s own banked stool restored it within days. That study measured composition, not symptoms, so track recovery with a dated symptom log and repeated measures of function.

    The course worked, the bloating left, and weeks later it came back. What refills a gut after antibiotics can be studied, and the part of you a stool report never sees can be measured.

    The question of probiotics after antibiotics tends to arrive the same week a course ends, when a patient wants something to put back. In The Weeds Were Never the Problem, the chapter video from The Angry Gut by Dr. Gurpreet Singh Padda, MD, MBA, MHP, and Ami Michelle Grimes, the example is a woman of fifty-five on her third round of treatment for small intestinal bacterial overgrowth. Each course cleared the problem. Each good stretch afterward was shorter than the last. That shrinking stretch is the most honest number in her chart, and it is one she can count herself.

    Probiotics after antibiotics: what the strongest study found

    The best test of that question followed people through three paths after a drug course: recover without help, take a multi-strain probiotic, or receive back their own stool, banked before the antibiotics. The capsule strains did settle into the gut lining. Yet compared with unaided recovery, the native community and the body’s own gene activity returned in a way the authors called markedly delayed and persistently incomplete. Autologous stool restored both within days.

    Read the limits before the headline. That study measured which organisms were present and what the gut tissue was expressing, not symptoms, infections or anything a patient feels. It does not prove a capsule makes a person sicker. It shows that adding a handful of passing strains is not the same as rebuilding a resident community, and that a supplement can slow the rebuild.

    Why an emptied gut refills with the wrong crowd

    An antibiotic removes more than the overgrowth. It also clears the residents that normally keep newcomers from taking hold, a defense called colonization resistance. The organisms quickest to return tolerate bile and oxygen and often carry resistance genes, while the bacteria that make butyrate, a fuel for the colon lining, grow slowly and strictly without oxygen. They lose a race that starts on an empty field.

    A deliberate experiment in healthy young men who took four days of three last-resort antibiotics showed the shape of it. Overall composition drifted back toward baseline within roughly six weeks. At 180 days, though, most of the men were still missing nine species that all of them had carried before treatment, and species holding beta-lactam resistance genes had been favored during the refill. The first brain, rebuilt by whatever arrives fastest, does not simply return to where it was, and the second brain lives downstream of that terrain.

    A stool report is a roster, not a function test

    Stool microbiome panels, breath tests and endoscopy are different tests done elsewhere. Measura [Cardiometabolic and Autonomic Health Analysis] does not sequence stool, measure intestinal gases or scope the bowel. That matters less than it sounds, because a list of names answers a narrower question than most people expect. In one capsule transplant trial in irritable bowel syndrome, the transplant measurably raised fecal diversity, and quality of life at three months still favored placebo. Membership rose. Function did not.

    The food data make the same point from the other side. In a trial of healthy adults who had taken no antibiotic, more than doubling fiber intake, from 21.5 to 45.1 grams a day, left diversity unchanged across the group. Eating 6.3 servings of fermented food a day raised it, and 19 of 93 inflammatory serum proteins fell, although that trial missed its own primary outcome. No study has yet tested fermented food for repopulation after an eradication course; that is a gap in trial design, not a verdict on the biology.

    Count the interval, not the organisms

    After one course cleared the breath test, the test was positive again at three months for 12.6% of patients, and the share climbed to 27.5% by six months and 43.7% by nine. Those three checkpoints are where recurrence was actually measured, so they are the sensible places to look again. Clearance and recovery also split apart: only 67.7% of patients with confirmed clearance reported feeling better.

    The predictors were not microbes. Long-term use of a proton pump inhibitor, an acid-reducing drug, raised the odds of recurrence more than threefold, and a history of appendix removal carried close to six times the odds. Whether an acid reducer is still needed is a conversation for the prescribing physician, never a reason to stop one alone. There is an economic tilt as well: a branded antibiotic comes with trials, packaging and a sales force, while a jar of fermented milk has no sponsor, so what goes back in after the drug rarely gets studied or discussed. For years the kill got counted as the win, and the good weeks were nobody’s metric.

    What Measura can put a number on while the gut rebuilds

    Measura measures the host rather than the microbes. Judged by function, recovery is what your body does across those months, and several parts of that are measurable. Laboratory panels put metabolic and inflammatory markers in front of your physician, the metaflammation picture a gut-focused workup often leaves out. Bioimpedance body composition tracks muscle and fat compartments, which matters when months of symptoms have reshaped how and what someone eats. Heart rate variability describes autonomic tone, the nervous system’s regulation of heart rhythm and recovery.

    None of these tells anyone whether overgrowth has returned; that remains a breath test your physician orders elsewhere. What they provide is a record of how you are functioning at the same checkpoints, so a flat breath test and a body that is still struggling are not confused with each other. Findings go to your physician. Keep your own log alongside: how many good weeks the last course bought, written as a number. The studies behind every figure here, with their populations and limits, are in the chapter companion, and the case for measuring before treating comes first.

    Frequently asked questions

    Should I take a probiotic capsule after a course of antibiotics?

    The strongest study of that question found a multi-strain capsule delayed the return of the gut’s native community compared with recovering unaided, while a transplant of the person’s own banked stool restored it within days. It measured composition and gene activity rather than symptoms, so it is not proof of harm. Fermented food has not been tested in this setting. Discuss options with your physician. Questions worth asking your doctor can help frame that visit.

    Can a stool test show whether my gut has recovered?

    It can list which organisms are present, not how well your gut or the rest of you is working. In one transplant trial, fecal diversity rose while quality of life favored placebo. Stool and breath tests are done elsewhere and are not Measura tests. A dated symptom log and repeated measures of function answer more of the question. See what a test result can and cannot tell you.

    Why does the bloating come back weeks after antibiotics work?

    The course removes the overgrowth and the resident bacteria that were holding the line, and fast-growing organisms move into the space first. In one cohort, breath tests turned positive again in nearly half of patients by nine months. Long-term acid-reducing medication and a prior appendectomy predicted that return. Raise both with your physician. Understanding your results explains how findings are reviewed together.

    What can Measura measure during gut recovery?

    Not the microbes. Measura measures the person carrying them: laboratory panels for the metabolic and inflammatory picture, bioimpedance for muscle and fat compartments, and heart rate variability for autonomic tone. Repeated at intervals your physician chooses, these build a record of function while the gut rebuilds, which is the standard recovery should be judged by. See who should be tested.

    Is fecal transplant an option after repeated antibiotic courses?

    It is established for recurrent Clostridioides difficile infection, where 13 of 16 patients cleared after donor stool, compared with 4 of 13 given vancomycin alone. Outside that infection, trials disagree, and regulators have reported serious transmitted infections after the procedure, including deaths. It is a specialist decision, not a supplement choice. The physician view of the relapse curve is written for the clinician.

    Track the recovery that counts

    Ask about laboratory, body composition and heart rate variability testing so your physician can follow how you function while your gut rebuilds.

    4477 Woodson Rd, Suite 201, St. Louis, MO 63134. Monday to Friday, 9:00 a.m. to 5:00 p.m. Please do not send symptoms, diagnoses or images through a web form — a website form is not a secure medical channel. Send your name and number and we will call you back.

    References

    • Suez, J., Zmora, N., Zilberman-Schapira, G., Mor, U., Dori-Bachash, M., Bashiardes, S., Zur, M., Regev-Lehavi, D., Ben-Zeev Brik, R., Federici, S., Horn, M., Cohen, Y., Moor, A. E., Zeevi, D., Korem, T., Kotler, E., Harmelin, A., Itzkovitz, S., Maharshak, N., … Elinav, E. (2018). Post-antibiotic gut mucosal microbiome reconstitution is impaired by probiotics and improved by autologous FMT. Cell, 174(6), 1406-1423.e16. https://doi.org/10.1016/j.cell.2018.08.047
    • Caballero-Flores, G., Pickard, J. M., & Núñez, G. (2022). Microbiota-mediated colonization resistance: mechanisms and regulation. Nature Reviews Microbiology, 21(6), 347-360. https://doi.org/10.1038/s41579-022-00833-7
    • Palleja, A., Mikkelsen, K. H., Forslund, S. K., Kashani, A., Allin, K. H., Nielsen, T., Hansen, T. H., Liang, S., Feng, Q., Zhang, C., Pyl, P. T., Coelho, L. P., Yang, H., Wang, J., Typas, A., Nielsen, M. F., Nielsen, H. B., Bork, P., Wang, J., … Pedersen, O. (2018). Recovery of gut microbiota of healthy adults following antibiotic exposure. Nature Microbiology, 3(11), 1255-1265. https://doi.org/10.1038/s41564-018-0257-9
    • Halkjær, S. I., Christensen, A. H., Lo, B. Z. S., Browne, P. D., Günther, S., Hansen, L. H., & Petersen, A. M. (2018). Faecal microbiota transplantation alters gut microbiota in patients with irritable bowel syndrome: results from a randomised, double-blind placebo-controlled study. Gut, 67(12), 2107-2115. https://doi.org/10.1136/gutjnl-2018-316434
    • Wastyk, H. C., Fragiadakis, G. K., Perelman, D., Dahan, D., Merrill, B. D., Yu, F. B., Topf, M., Gonzalez, C. G., Van Treuren, W., Han, S., Robinson, J. L., Elias, J. E., Sonnenburg, E. D., Gardner, C. D., & Sonnenburg, J. L. (2021). Gut-microbiota-targeted diets modulate human immune status. Cell, 184(16), 4137-4153.e14. https://doi.org/10.1016/j.cell.2021.06.019
    • Lauritano, E. C., Gabrielli, M., Scarpellini, E., Lupascu, A., Novi, M., Sottili, S., Vitale, G., Cesario, V., Serricchio, M., Cammarota, G., Gasbarrini, G., & Gasbarrini, A. (2008). Small intestinal bacterial overgrowth recurrence after antibiotic therapy. The American Journal of Gastroenterology, 103(8), 2031-5. https://doi.org/10.1111/j.1572-0241.2008.02030.x
    • Gatta, L., & Scarpignato, C. (2017). Systematic review with meta-analysis: Rifaximin is effective and safe for the treatment of small intestine bacterial overgrowth. Alimentary Pharmacology & Therapeutics, 45(5), 604-616. https://doi.org/10.1111/apt.13928
    • van Nood, E., Vrieze, A., Nieuwdorp, M., Fuentes, S., Zoetendal, E. G., de Vos, W. M., Visser, C. E., Kuijper, E. J., Bartelsman, J. F. W. M., Tijssen, J. G. P., Speelman, P., Dijkgraaf, M. G. W., & Keller, J. J. (2013). Duodenal infusion of donor feces for recurrent Clostridium difficile. The New England Journal of Medicine, 368(5), 407-15. https://doi.org/10.1056/NEJMoa1205037

    Related reading







